
Treatment for uterine cancer is based on the type and characteristics of the cancer, how far it has progressed, your overall health and the priorities that matter to you. At Saint John’s Cancer Institute, our multidisciplinary team develops an individualized treatment plan that may include surgery, radiation therapy, systemic treatment or a combination of approaches.

Endometrial cancer, which begins in the lining of the uterus, accounts for most uterine cancers. Uterine sarcomas are much less common and develop in the muscle or other supporting tissues of the uterus. Because these cancers can behave differently, treatment recommendations depend first on the specific type of uterine cancer you have.
This page describes treatments that may be used for uterine cancers, including endometrial cancer. Your gynecologic oncologist will recommend an approach based on your diagnosis and the individual characteristics of your cancer. Learn more about Endometrial Cancer and Uterine Cancer.
Surgery for Uterine and Endometrial Cancer
Surgery is an important treatment for many uterine cancers and is often the primary treatment for endometrial cancer that has not spread extensively. The operation most commonly includes a hysterectomy to remove the uterus and cervix. Depending on the type and extent of cancer, the fallopian tubes and ovaries may also be removed, and lymph nodes may be evaluated to determine whether cancer has spread.
When appropriate, surgery may be performed using minimally invasive techniques, including robot-assisted surgery. These approaches allow the surgeon to perform complex procedures through smaller incisions and can offer recovery advantages for appropriately selected patients. The surgical approach is based on the cancer, the extent of surgery required and individual patient considerations.
Evaluating Lymph Nodes
Assessing nearby lymph nodes can provide important information about whether cancer has spread and may help guide treatment after surgery. Depending on the clinical situation, this may involve sentinel lymph node mapping or removal of selected lymph nodes for examination by a pathologist.
During sentinel lymph node mapping, a fluorescent dye such as indocyanine green may be injected into the cervix to help the surgeon identify the first lymph nodes to which cancer would be most likely to spread. The appropriate approach to lymph node evaluation depends on the type and characteristics of the cancer and the planned surgery.
What to Expect After Uterine Cancer Surgery
Recovery after surgery varies according to the type of procedure, whether surgery is minimally invasive or open, your overall health and the extent of surgery required. Your surgical team will provide specific instructions for recovery, activity and follow-up based on your procedure.

- Hospital stay and early recovery: Some patients can return home relatively soon after minimally invasive surgery, while more extensive procedures may require a longer hospital stay and recovery period.
- Pain and discomfort: Your care team will help manage discomfort after surgery and provide instructions for medications and other strategies that can support recovery.
- Incision and vaginal care: You will receive instructions about caring for surgical incisions, vaginal discharge or bleeding, bathing and signs that should prompt a call to your care team.
- Movement and blood clot prevention: Walking and gradually increasing activity are often encouraged after surgery. Depending on your individual risk, additional measures may be recommended to help prevent blood clots.
- Bowel and bladder function: Anesthesia, medications and changes in activity can temporarily affect bowel or bladder function. Your care team can recommend ways to manage these changes during recovery.
- Returning to normal activities: Your surgeon will advise when it is appropriate to resume driving, exercise, work, sexual activity and other regular activities.
- Pathology and follow-up: After surgery, your care team will review the final pathology findings with you and explain whether additional treatment or monitoring is recommended.
Radiation Therapy for Uterine and Endometrial Cancer
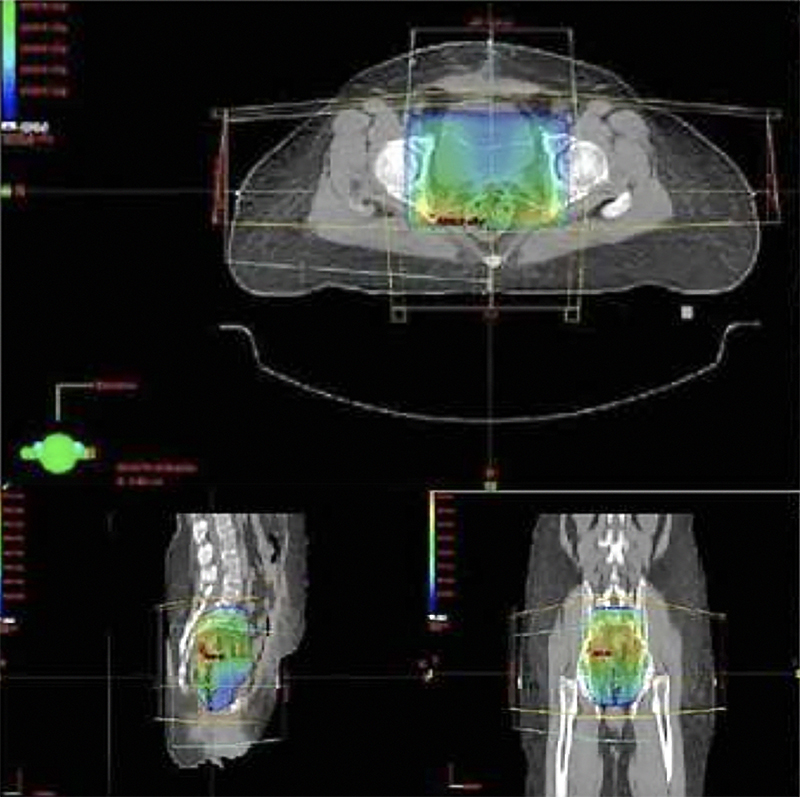
Radiation therapy uses high-energy radiation to destroy cancer cells in a specific area of the body. It may be recommended after surgery to reduce the risk of cancer returning, as part of treatment for more advanced disease, or when surgery is not appropriate. Radiation may also be used in selected situations to control cancer that has returned or to relieve symptoms.
Radiation treatment for uterine and endometrial cancer may include external beam radiation therapy, which delivers radiation from outside the body, and vaginal brachytherapy, which delivers radiation internally near the area being treated. The type and timing of radiation depend on the cancer and your individual treatment plan.
Learn more about Vasek Polak Radiation Oncology at Saint John’s Health Center.
Chemotherapy for Uterine and Endometrial Cancer
Chemotherapy uses medications that travel through the bloodstream to destroy cancer cells or interfere with their ability to grow and divide. It may be recommended for some higher-risk endometrial cancers, cancers that have spread beyond the uterus, recurrent disease and certain uterine sarcomas.
Chemotherapy may be given after surgery, alone or in combination with radiation therapy or other systemic treatments. The medications and sequence of treatment depend on the specific type and characteristics of the cancer, previous treatment, your overall health and other clinical factors.
Targeted Therapy for Uterine and Endometrial Cancer
Targeted therapies are designed to interfere with specific molecules or pathways that help cancer cells grow or survive. Testing of the tumor can sometimes identify characteristics that help your oncologist determine whether a targeted treatment may be appropriate.
Targeted therapy is used primarily in selected advanced or recurrent uterine and endometrial cancers and may be given alone or with other systemic treatments. Because eligibility depends on the particular cancer and its molecular characteristics, your oncologist can explain whether tumor testing identifies a treatment target relevant to your care.
Immunotherapy for Uterine and Endometrial Cancer
Immunotherapy helps the immune system recognize and attack cancer cells. It has become an important treatment option for some patients with advanced or recurrent endometrial cancer and may be used alone or in combination with other treatments depending on the clinical situation.
Molecular and biomarker testing can help determine whether particular immunotherapy approaches may be appropriate. Your oncologist will consider these findings together with the stage of the cancer, previous treatment and other factors when developing your treatment plan.
Hormone Therapy for Uterine and Endometrial Cancer

Some uterine cancers use hormones to support their growth. Hormone therapy can slow or control the growth of certain hormone-sensitive cancers by changing hormone activity in the body or interfering with the way cancer cells respond to hormones.
Hormone therapy may be considered for selected endometrial cancers and certain uterine sarcomas, particularly when tumor characteristics indicate that the cancer may respond to this approach. It may also have a role in fertility-sparing treatment for carefully selected patients with early endometrial cancer.
Fertility-Sparing Treatment for Endometrial Cancer
Standard surgical treatment for endometrial cancer generally involves removal of the uterus, which means pregnancy is no longer possible. For some younger patients with carefully selected early, low-risk endometrial cancers who wish to preserve fertility, treatment with hormone therapy while keeping the uterus may be considered.
Fertility-sparing treatment is not appropriate for every endometrial cancer and requires careful evaluation and close monitoring by a gynecologic oncologist. If future pregnancy is important to you, discussing fertility before treatment begins can help your care team determine whether fertility preservation is medically appropriate and what options may be available.
Finding the Right Treatment Approach
There is no single treatment plan that is appropriate for every uterine or endometrial cancer. Your care team considers the type and stage of cancer, pathology and molecular findings, previous treatment, your overall health and your individual needs and priorities when recommending treatment.
As additional information becomes available through surgery, pathology, imaging or molecular testing, your treatment plan may be refined. Your gynecologic oncologist can explain why a particular approach is being recommended, what alternatives may be appropriate and what you can expect as treatment moves forward.
Questions About Uterine and Endometrial Cancer Treatment
Understanding why a particular treatment is being recommended can help you prepare for care and participate in decisions that affect you. Because uterine cancers can differ considerably in their behavior and treatment, your gynecologic oncologist can help you understand which options apply to your diagnosis and what you can expect before, during and after treatment.
You may find it helpful to bring a family member, friend or other support person to your consultation and write down questions beforehand. The following questions can help guide conversations with your care team.
What are my treatment options, and why are you recommending this approach?
Your treatment plan is based on the specific type of uterine cancer, its stage and other characteristics, as well as your overall health and individual priorities. Ask your oncologist which treatments are being considered, what each treatment is intended to accomplish and why the recommended approach is appropriate for your particular cancer. Understanding the alternatives can also help you weigh the potential benefits and risks of each option.

What side effects should I expect from treatment?
Side effects depend on the treatment you receive and can vary considerably from one person to another. Ask about both short- and long-term effects, which symptoms are expected, which should prompt a call to your care team, and what medications, supportive care or other strategies are available to help manage them.
How could treatment affect my daily life?
Surgery, radiation therapy and systemic treatments can temporarily or sometimes permanently affect aspects of daily life. Before treatment begins, discuss what to expect regarding recovery, work, exercise, driving, sexual health, menopause, fertility and other activities that are important to you. Planning ahead can also help you identify when additional support at home or work may be useful.
What is the likelihood that my cancer could return?
The risk of recurrence is different for each patient and depends on factors such as the type, stage and characteristics of the cancer and the treatment received. Your oncologist can explain what is known about your individual risk, how that information influenced the recommended treatment and what follow-up will be needed after treatment is completed.
Should I consider a clinical trial?
Clinical trials study new treatments, new combinations of treatments and new ways of using existing therapies. Depending on your diagnosis and where you are in treatment, a clinical trial may provide an additional option to consider. Participation is voluntary, and your care team can explain the purpose of an appropriate trial, how it differs from standard treatment and what participation would involve.
How can symptoms and side effects be managed during and after treatment?
Managing symptoms and side effects is an important part of cancer care. Tell your care team about symptoms that affect your comfort, nutrition, sleep, mobility, sexual health, emotional well-being or ability to carry out daily activities. Supportive care can be provided alongside cancer treatment and may include medications, rehabilitation, nutritional guidance, emotional support and other services based on your needs.
Moving Forward With Uterine Cancer Treatment

You do not need to understand every treatment possibility before meeting with your care team. Knowing the basic characteristics of your cancer and bringing questions about the goals of treatment, your options and what matters most to you can help you participate in decisions and understand why a particular approach is being recommended.
As treatment progresses, recommendations may be refined as additional information becomes available through surgery, pathology, molecular testing, imaging or your response to treatment. Your gynecologic oncologist and other members of your care team can explain what new findings mean, answer questions as they arise and help you understand what comes next.
If you have questions regarding uterine cancer or would like an expert second opinion, please call today or click here to schedule an appointment.




