Center for Gastrointestinal and Hepatobiliary Tumors

The Center for Gastrointestinal and Hepatobiliary Tumors offers an internationally recognized comprehensive program that includes minimally invasive surgery and personalized care. Through clinical innovations, including robot-assisted surgery, patients return to normal activities more quickly.

JWCI GI Team Doctor talking to nurse Doctor talking with nurses

Personalized Care and Improved Quality of Life

Providence Saint John's Health Center in Santa Monica, California
Providence Saint John’s Health Center in Santa Monica provides evaluation and treatment for gastrointestinal and hepatobiliary conditions.

The Center for Gastrointestinal and Hepatobiliary Tumors at Saint John’s Cancer Institute provides evaluation and treatment for cancerous and noncancerous conditions affecting the digestive system, liver, and related organs. Our multidisciplinary approach brings together specialists who consider each patient’s diagnosis, overall health, and individual treatment needs.

From diagnostic evaluation and treatment planning through recovery and follow-up, our goal is to help patients understand their options and make informed decisions. Care may involve surgery, endoscopic procedures, systemic therapies, radiation therapy, or specialized techniques designed to address particular tumors and digestive disorders.

Coordinated Care for Complex Conditions

Gastrointestinal cancers and related conditions often require expertise from several clinical specialties. Depending on the diagnosis, a patient’s care may involve gastrointestinal and surgical oncologists, medical oncologists, radiation oncologists, gastroenterologists, radiologists, pathologists, and other specialists. Multidisciplinary evaluation helps clarify the diagnosis, identify available treatment approaches, and determine how different therapies may work together. It also supports planning for nutrition, symptom management, recovery, and ongoing care.

Some patients can be treated with a single procedure, while others benefit from surgery combined with chemotherapy, radiation therapy, immunotherapy, or targeted medications. For certain cancers, treatment before surgery may improve the overall approach or help determine whether an operation is appropriate. When a condition cannot be cured, treatment can still focus on controlling disease, relieving symptoms, and preserving quality of life.

Research, Clinical Trials, and Individualized Treatment

Research at Saint John's Cancer Institute aims to improve patient outcomes
Research at Saint John’s Cancer Institute aims to improve patient outcomes for many types of cancer.

Research contributes to the continuing development of diagnostic methods, surgical techniques, cancer medications, and minimally invasive procedures. Saint John’s Cancer Institute supports clinical and translational research intended to improve understanding of cancer biology and treatment. When an appropriate study is available, eligible patients may have the opportunity to discuss clinical trial participation with their care team. Clinical trials are not suitable for everyone, and participation depends on the study requirements, diagnosis, and individual circumstances.

Individualized care also considers the biological characteristics of a tumor. Molecular and genetic testing may help guide treatment for certain gastrointestinal cancers, identify hereditary cancer risks, or determine eligibility for selected medications and clinical studies. These findings are interpreted alongside imaging, pathology, disease stage, and the patient’s overall health.
GI and Hepatobiliary Conditions

The Center for Gastrointestinal and Hepatobiliary Tumors evaluates conditions affecting the esophagus, stomach, pancreas, liver, colon, and rectum. These include cancers arising within the digestive system, tumors that spread to the liver from other organs, and selected benign disorders affecting swallowing and digestion. Understanding the condition, its extent, and its potential effects on other organs is an important first step in developing an appropriate treatment plan.

Benign Esophageal Disease

Benign esophageal diseases are noncancerous conditions that may interfere with swallowing, cause acid reflux, or produce inflammation and narrowing of the esophagus. Common examples include gastroesophageal reflux disease (GERD), achalasia, esophageal strictures, hiatal hernias, and diverticula. Symptoms may include heartburn, regurgitation, difficulty swallowing, or the sensation that food is becoming stuck. Barrett’s esophagus is a separate condition associated with chronic reflux that can increase the risk of esophageal adenocarcinoma, although most patients with Barrett’s do not develop cancer. Evaluation may include upper endoscopy, imaging, esophageal manometry, or reflux testing depending on the symptoms and suspected disorder.

Learn more about Benign Esophageal Disease.

Colorectal Cancer

Medical illustration accompanying gastrointestinal diagnostic evaluation
Diagnostic evaluation helps determine the type and extent of gastrointestinal disease before treatment planning.

Colorectal cancer develops in the colon or rectum and frequently begins as abnormal growths called polyps. Many polyps are benign, but certain types can develop into cancer over time, making screening and early detection especially important. Symptoms may include rectal bleeding, changes in bowel habits, unexplained anemia, abdominal discomfort, or unintended weight loss, although early cancers may cause no symptoms. Colonoscopy allows physicians to examine the bowel, remove many polyps, and obtain tissue samples for diagnosis. When cancer is identified, additional testing helps determine its stage and whether treatment should differ for a colon or rectal tumor.

Learn more about Colorectal Cancer.

Esophageal Cancer

Esophageal cancer develops in the tissues of the esophagus, the muscular tube that carries food from the throat to the stomach. The two principal types are adenocarcinoma and squamous cell carcinoma, which differ in their usual locations, risk factors, and certain treatment considerations. Difficulty swallowing, painful swallowing, unintended weight loss, and persistent discomfort may develop as the disease progresses. Risk factors include tobacco use, heavy alcohol consumption for squamous cell carcinoma, and chronic reflux or Barrett’s esophagus for adenocarcinoma. Diagnosis generally involves upper endoscopy with biopsy, followed by imaging and other testing to determine the extent of disease.

Learn more about Esophageal Cancer.

Liver Cancer

Liver-cancer-saint-johns-cancer-institute
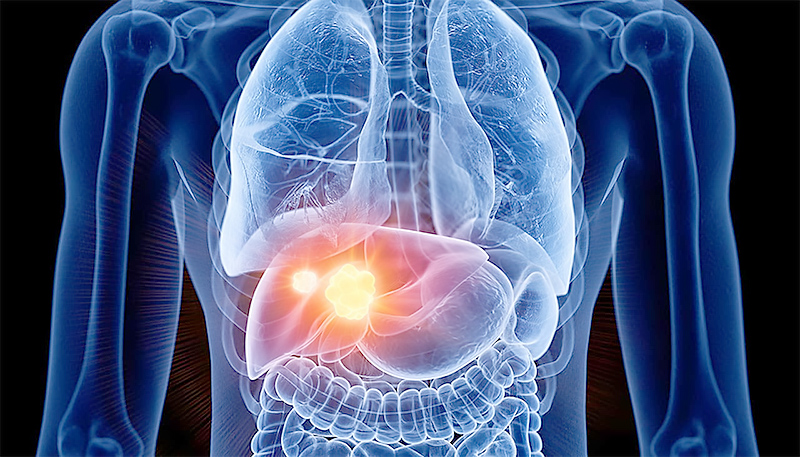
Many patients may not present with symptoms of liver cancer until the disease has progressed.

Liver tumors may begin within the liver or develop when cancer from another organ spreads to liver tissue. Primary liver cancers include hepatocellular carcinoma, which is often associated with chronic liver disease, and intrahepatic cholangiocarcinoma, which develops from bile ducts within the liver. Other cancers, including colorectal cancer, can produce metastatic tumors in the liver that require treatment based partly on their original site. Many liver tumors cause few symptoms initially, although abdominal discomfort, weight loss, jaundice, or changes in liver function may occur. Diagnosis and staging require consideration of imaging findings, tumor characteristics, underlying liver disease, and the amount of healthy liver tissue available.

Learn more about Liver Cancer.

Pancreatic Cancer

Pancreatic cancer develops in the pancreas, an organ involved in digestion and blood sugar regulation. Pancreatic ductal adenocarcinoma is the most common type, while pancreatic neuroendocrine tumors are less common and behave differently. Symptoms can include unexplained weight loss, abdominal or back pain, jaundice, changes in digestion, or new-onset diabetes, but early disease may be difficult to recognize. Evaluation commonly involves specialized CT or MRI imaging, endoscopic ultrasound, and tissue sampling when appropriate. Determining whether the cancer involves nearby blood vessels or has spread beyond the pancreas is essential for understanding treatment options.

Learn more about Pancreatic Cancer.

Stomach Cancer

Stomach cancer, also called gastric cancer, most commonly develops from glandular cells lining the stomach. Risk factors include Helicobacter pylori infection, certain chronic stomach conditions, tobacco use, and some inherited cancer syndromes. Early disease may produce few symptoms, while more advanced cancer can cause persistent abdominal discomfort, reduced appetite, unexplained weight loss, anemia, or bleeding. Upper endoscopy with biopsy is central to establishing the diagnosis, with imaging and other testing used to determine the extent of cancer. Tumors near the junction between the stomach and esophagus require particular attention because their classification and treatment may overlap with those of esophageal cancer.

Learn more about Stomach Cancer.

Explore Patient Resources and Links. Please see Patient Resources.

GI and Hepatobiliary Treatment

Treatment of gastrointestinal and hepatobiliary conditions may involve surgery, endoscopic procedures, chemotherapy, immunotherapy, targeted medications, radiation therapy, or specialized tumor-directed technologies. Some conditions can be treated with a single intervention, while others require therapies coordinated over several months. The appropriate approach depends on the diagnosis, disease extent, available clinical evidence, and the patient’s overall health and goals.

Benign Esophageal Disease Treatment

Treatment for benign esophageal disorders focuses on relieving symptoms, improving swallowing, reducing inflammation, and addressing structural or functional abnormalities. Patients with reflux or inflammatory conditions may benefit from dietary changes, medications, or other nonsurgical approaches. Endoscopic dilation can help certain esophageal narrowings, while achalasia may require procedures such as myotomy or pneumatic dilation. Selected patients with significant reflux or hiatal hernias may benefit from minimally invasive surgery. Surveillance and endoscopic treatment may also be appropriate for Barrett’s esophagus when precancerous changes are identified.

Learn more about Benign Esophageal Disease Treatment.

Colorectal Cancer Treatment

Partial colectomy and resection of the colon - saint johns cancer institute
In partial colectomy, one or more parts of the colon are removed surgically then rejoined.

Many localized colon and rectal cancers are treated surgically, with the procedure selected according to the tumor’s location and extent. Some patients require chemotherapy before or after surgery, while radiation therapy is particularly important for selected rectal cancers. Modern treatment planning considers whether bowel function and normal anatomy can be preserved without compromising cancer treatment. Immunotherapy and targeted medications may benefit patients whose tumors have specific molecular characteristics. For selected patients with metastatic disease, treatment may also include procedures directed at tumors in organs such as the liver or lungs.

Learn more about Colorectal Cancer Treatment.

Esophageal Cancer Treatment

Esophageal cancer treatment depends on whether the tumor is adenocarcinoma or squamous cell carcinoma, its location, and the extent of disease. Certain early cancers may be removed endoscopically, while many locally advanced tumors require chemotherapy, radiation therapy, surgery, or combinations of these approaches. Esophagectomy removes the affected portion of the esophagus and reconstructs the digestive tract, sometimes using minimally invasive or robot-assisted techniques. Immunotherapy and selected targeted treatments may be appropriate according to tumor characteristics and previous treatment. Maintaining nutrition and swallowing function is an important part of care throughout treatment and recovery.

Learn more about Esophageal Cancer Treatment.

Liver Cancer Treatment

Illustration of robot-assisted liver surgery
Selected liver tumors may be removed using minimally invasive, robot-assisted surgical techniques.

Management of liver tumors depends on whether the cancer originates in the liver or has spread from another organ, as well as the amount of healthy liver tissue available. Selected patients may benefit from surgical resection, transplantation, or localized procedures that destroy or control individual tumors. Liver-directed treatments can include thermal ablation, focused ultrasound histotripsy, embolization, radioembolization, and stereotactic radiation therapy. Immunotherapy, targeted medications, and chemotherapy may also play a role according to the cancer type and stage. Multidisciplinary planning helps balance cancer treatment with preservation of liver function.

Learn more about Liver Cancer Treatment.

Pancreatic Cancer Treatment

Pancreatic cancer treatment often requires careful coordination between surgery and systemic therapies. For selected localized tumors, procedures such as the Whipple operation or distal pancreatectomy may offer an opportunity for long-term disease control. Chemotherapy is commonly used before or after surgery and is a principal treatment for many patients with locally advanced or metastatic disease. Radiation therapy and biomarker-guided medications may be appropriate in particular circumstances. Supportive care addresses nutrition, digestive function, pain, and other challenges that can arise during treatment and recovery.

Learn more about Pancreatic Cancer Treatment.

Stomach Cancer Treatment

Stomach cancer treatment depends on tumor location, stage, and molecular characteristics. Selected early cancers may be treated endoscopically, while other localized tumors require partial or total gastrectomy, often combined with chemotherapy. Immunotherapy and targeted medications may benefit patients with particular tumor biomarkers, and radiation therapy is used in selected circumstances. Specialized intraperitoneal treatments remain under investigation for some patients with cancer involving the abdominal lining. Nutritional counseling and long-term monitoring are especially important after stomach surgery because digestion and nutrient absorption can change significantly.

Learn more about Stomach Cancer Treatment.

Explore Patient Resources and Links. Please see Patient Resources.

Technology Spotlight

:

Focused Ultrasound Histotripsy

Histotripsy for liver cancer
Histotripsy (by HistoSonics) for liver cancer at Saint John’s Health Center

Histotripsy is a noninvasive, image-guided treatment that uses focused ultrasound pulses to mechanically destroy selected liver tumors. Unlike conventional thermal ablation, which relies on heating or freezing tissue, histotripsy creates microscopic gas bubbles whose rapid expansion and collapse disrupt the targeted tissue. Because ultrasound energy is delivered from outside the body, treatment does not require surgical incisions or insertion of an ablation needle into the tumor. This technology may provide another localized treatment option for appropriately selected patients with primary or metastatic liver tumors.

Histotripsy is not suitable for every liver tumor. Treatment depends on whether the tumor can be adequately visualized and targeted, its location relative to nearby structures, liver function, and the patient’s overall cancer treatment plan. Research continues to evaluate long-term cancer control, patient selection, and how histotripsy compares with established liver-directed procedures. Its potential benefits should therefore be considered alongside surgery, thermal ablation, radiation, embolization, and systemic therapies rather than as a universal replacement for them.

Learn more about Histotripsy for Liver Tumors, including how the technology works and which patients may be candidates.

Featured Patient Testimonial

Audrey Brooks shares her experience with pancreatic cancer, the Whipple procedure, and recovery following an unexpected postoperative cardiac arrest at Providence Saint John’s Health Center.

Diagnosed with early-stage pancreatic cancer, Audrey underwent a Whipple procedure performed by Dr. Anton Bilchik. The following day, she experienced a life-threatening cardiac arrest. In this video, Audrey reflects on her treatment, recovery, and the people who supported her through an extraordinary experience.

Read Audrey’s pancreatic cancer patient story.

At Saint John’s Cancer Institute, our approach to gastrointestinal and hepatobiliary care combines multidisciplinary clinical expertise with individualized treatment planning. We recognize that every diagnosis brings different medical needs, questions, and decisions for patients and their families.

From understanding a diagnosis to considering treatment options and managing recovery, our goal is to provide clear information, coordinated care, and support throughout the patient journey.

If you have questions about gastric symptoms or digestion related conditions, please call today. Click here to request an appointment.