
What Is Esophageal Cancer?
Esophageal cancer develops in the esophagus, the muscular tube that carries food and liquids from the throat to the stomach. Cancer can arise anywhere along the esophagus, including near its connection to the stomach, known as the gastroesophageal junction. At Saint John’s Health Center, our specialists provide multidisciplinary evaluation and individualized treatment planning for patients with esophageal cancer, including medical, surgical, and radiation-based approaches when appropriate.
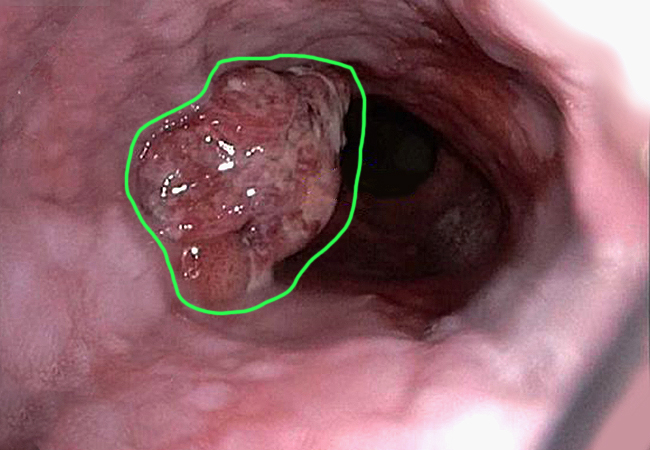
Most esophageal cancers develop in the inner lining of the esophagus. As the disease progresses, a tumor may grow into deeper layers of the esophageal wall, involve nearby lymph nodes, or spread to distant organs such as the liver or lungs.
The two most common types are adenocarcinoma and squamous cell carcinoma. Adenocarcinoma frequently develops in the lower esophagus, near the stomach, while squamous cell carcinoma can occur throughout the esophagus and is more commonly found in its upper and middle portions.
Esophageal cancer is relatively uncommon in the United States, and there is no standard screening test recommended for the general population. However, individuals with certain risk factors or precancerous conditions, such as Barrett’s esophagus, may benefit from specialized evaluation and surveillance.
Early esophageal cancer may cause few or no symptoms. As a tumor grows, difficulty swallowing often develops, initially affecting solid foods and sometimes progressing to liquids. Other symptoms may include painful swallowing, persistent chest discomfort, regurgitation, unexplained weight loss, coughing, or hoarseness.
Evaluation and Diagnosis
Diagnosing esophageal cancer begins with a review of symptoms, medical history, and a physical examination. Persistent or progressive difficulty swallowing is an important reason to seek medical evaluation, particularly when accompanied by unexplained weight loss or other concerning symptoms.
Upper gastrointestinal endoscopy (EGD) is a principal diagnostic procedure. A gastroenterologist uses a flexible instrument equipped with a small camera to examine the esophageal lining and obtain tissue biopsies from suspicious areas. A pathologist examines the tissue to confirm the diagnosis and identify the type of cancer.
Additional testing helps determine how deeply the tumor extends, whether lymph nodes are involved, and whether cancer has spread beyond the esophagus.
Diagnostic Imaging and Staging
- Endoscopic Ultrasound (EUS): Uses ultrasound imaging during endoscopy to help evaluate tumor depth and nearby lymph nodes when appropriate.
- Computed Tomography (CT): Produces detailed images of the chest, abdomen, and sometimes pelvis to assess the tumor and possible spread.
- PET/CT: Combines metabolic and anatomical imaging to help identify cancer in lymph nodes or distant organs that may not be apparent on other studies.
- Barium Swallow (Esophagram): Uses fluoroscopic X-ray imaging to examine swallowing and identify narrowing or obstruction within the esophagus.
- Additional Procedures: Selected patients may require further tissue sampling or minimally invasive staging procedures to clarify findings before treatment.
The results help establish the cancer stage and determine whether the treatment goal is to remove or eliminate the cancer, control its growth, or relieve symptoms. Not every patient requires every diagnostic procedure.

Factors That May Affect Treatment
Esophageal cancer treatment is individualized. A multidisciplinary team may review imaging, biopsy findings, overall health, and treatment goals when recommending an approach.
- The type of cancer, including adenocarcinoma or squamous cell carcinoma
- The tumor’s location and extent within the esophagus or gastroesophageal junction
- Whether nearby lymph nodes or distant organs are involved
- Molecular or biomarker findings that may guide systemic therapy
- Age, general health, nutritional status, and ability to tolerate treatment
- Previous medical conditions or cancer treatments
- Expected benefits and possible side effects of available therapies
- Patient preferences and goals of care
These factors help determine whether surgery, chemotherapy, radiation therapy, immunotherapy, targeted medication, or a combination of treatments is appropriate.
What Causes Esophageal Cancer?
Esophageal cancer develops when cells acquire genetic changes that allow them to grow and divide abnormally. Over time, these cells may form a tumor that invades nearby tissues or spreads to other parts of the body.
The exact cause is not always known. However, several medical conditions, environmental exposures, and lifestyle factors are associated with an increased risk. These factors differ between the two principal types of esophageal cancer.
Types of Esophageal Cancer
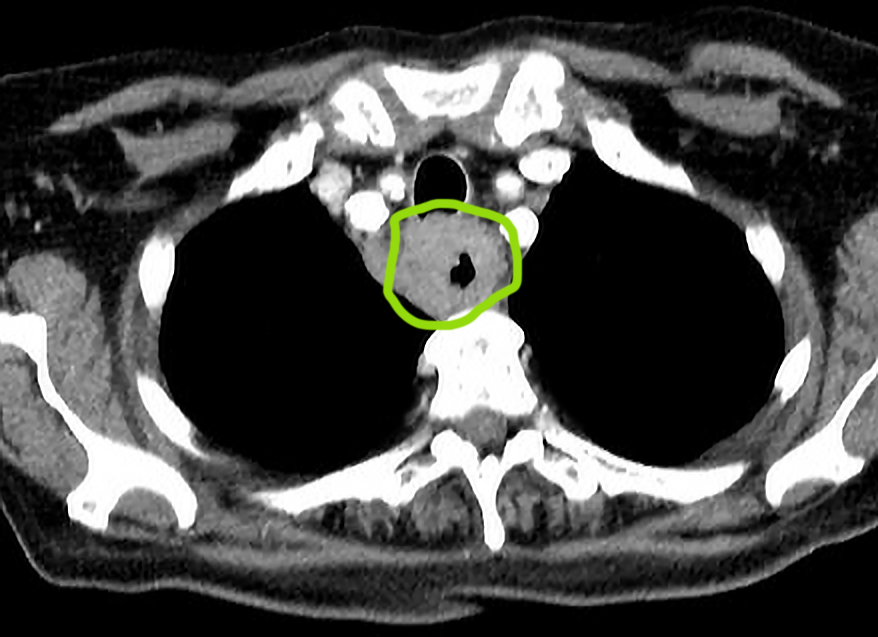
The type of esophageal cancer is determined by the cells in which it develops. Identifying the tumor type is essential because adenocarcinoma and squamous cell carcinoma have different patterns of occurrence and may require different treatment approaches.
Adenocarcinoma
Adenocarcinoma develops from gland-forming cells, often in tissue that has undergone changes associated with longstanding gastroesophageal reflux. It most frequently occurs in the lower portion of the esophagus or near the gastroesophageal junction.
Esophageal adenocarcinoma is more common among men in the United States and is associated with risk factors including chronic reflux, Barrett’s esophagus, obesity, and tobacco exposure.
Squamous Cell Carcinoma
Squamous cell carcinoma develops from the thin, flat squamous cells that normally line the esophagus. It commonly occurs in the upper or middle portions of the esophagus, although it can develop elsewhere.
Squamous cell carcinoma is the most common type of esophageal cancer worldwide. Important risk factors include tobacco use, heavy alcohol consumption, and certain other environmental or nutritional exposures.
Rare tumors involving the esophagus include neuroendocrine carcinomas, lymphomas, sarcomas, and other uncommon malignancies. These tumors may require specialized evaluation and treatment that differs from conventional esophageal cancer care.
Gastroesophageal Junction (GEJ) Cancer
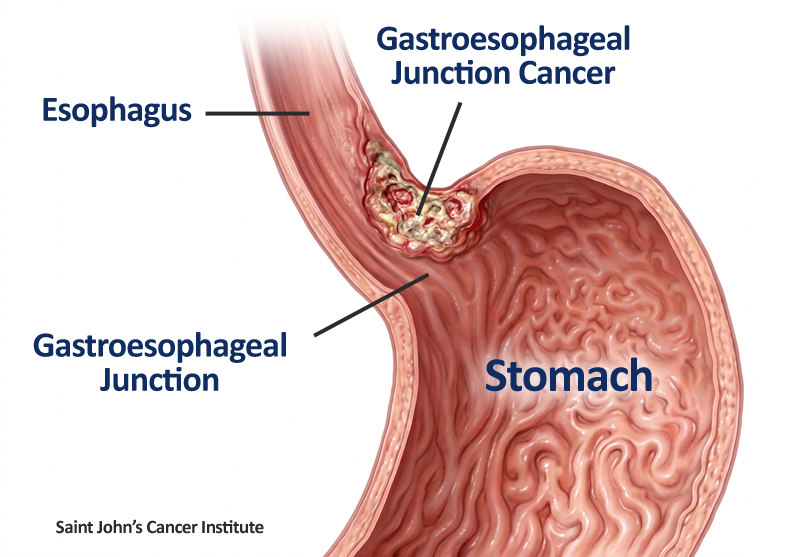
The gastroesophageal junction is the area where the lower esophagus connects to the upper stomach. Cancer developing in this region may involve both organs, making the tumor’s precise location an important consideration in diagnosis, staging, and treatment planning.
Most gastroesophageal junction cancers are adenocarcinomas. Depending on where the tumor originates and how far it extends into the esophagus or stomach, it may be classified and treated similarly to esophageal cancer or gastric (stomach) cancer.
Treatment may involve surgery, chemotherapy, radiation therapy, immunotherapy, or targeted medication, depending on the stage, tumor characteristics, and patient’s overall health. Surgical planning can be particularly important because removing a tumor in this region may require reconstruction involving the esophagus and stomach.
Learn more about Stomach Cancer, including tumors affecting the upper stomach near the gastroesophageal junction.
What Are the Risk Factors for Esophageal Cancer?
Risk factors differ according to the type of esophageal cancer. Having one or more risk factors does not mean a person will develop cancer, and esophageal cancer can occur in people without an obvious risk factor.
Risk factors associated with esophageal adenocarcinoma include longstanding gastroesophageal reflux disease (GERD), Barrett’s esophagus, obesity, smoking, older age, and male sex. Squamous cell carcinoma is more strongly associated with tobacco use, heavy alcohol consumption, and certain exposures, including frequently drinking very hot beverages.
Persistent difficulty swallowing, unexplained weight loss, painful swallowing, or worsening symptoms should be evaluated regardless of an individual’s known risk factors.
Barrett’s Esophagus
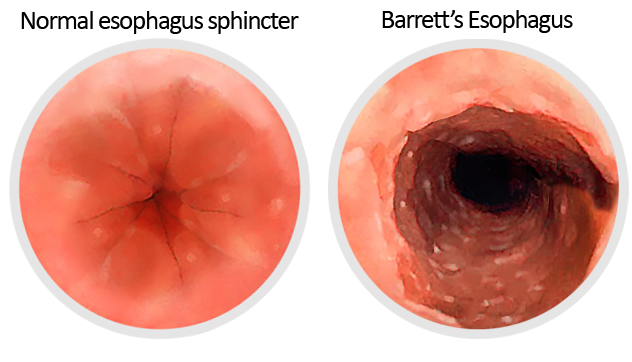
Barrett’s esophagus is a condition in which the normal lining of the lower esophagus is replaced by a different type of tissue, usually associated with prolonged exposure to stomach acid and other refluxed contents.
Barrett’s esophagus itself often produces no distinct symptoms, although patients may experience heartburn or regurgitation from underlying GERD. Most people with Barrett’s esophagus do not develop esophageal cancer, but the condition increases the risk of esophageal adenocarcinoma.
Upper endoscopy and tissue biopsies can identify Barrett’s esophagus and determine whether abnormal cellular changes, called dysplasia, are present. Depending on the findings, patients may require periodic surveillance or endoscopic treatment of precancerous tissue.
Gastroesophageal Reflux Disease (GERD)
Gastroesophageal reflux disease occurs when stomach contents repeatedly flow backward into the esophagus. This may happen when the lower esophageal sphincter, a muscular valve near the stomach, does not prevent reflux effectively.
GERD can cause heartburn, regurgitation, and inflammation of the esophageal lining. Over time, chronic reflux may contribute to Barrett’s esophagus in some patients, which can increase the risk of adenocarcinoma.
Most people with GERD will not develop esophageal cancer. However, persistent or worsening reflux symptoms, particularly when accompanied by difficulty swallowing, bleeding, or unexplained weight loss, warrant medical evaluation.
Tobacco, Alcohol, and Other Risk Factors
Smoking increases the risk of both major esophageal cancer types, while heavy alcohol consumption is particularly associated with squamous cell carcinoma. Using tobacco and alcohol together can further increase the risk of squamous cell cancer.
Maintaining a healthy weight, avoiding tobacco, limiting or avoiding alcohol, and seeking medical care for persistent reflux or swallowing difficulties are reasonable steps toward reducing risk and addressing concerning symptoms.
Can Esophageal Cancer Be Detected Early?
There is no standard screening test recommended for esophageal cancer in people at average risk. However, patients with Barrett’s esophagus or certain other high-risk conditions may benefit from periodic upper endoscopy or other specialized evaluation.
Early esophageal cancer may not cause noticeable symptoms, making appropriate surveillance particularly important for selected higher-risk patients. New or progressive difficulty swallowing, painful swallowing, or unexplained weight loss should prompt medical assessment rather than waiting for a routine screening appointment.
Esophageal Cancer Treatment
Esophageal cancer treatment depends on the type and stage of cancer, its location, whether it has spread, and the patient’s overall health. Treatment may involve surgery, chemotherapy, radiation therapy, immunotherapy, targeted medications, or a combination of approaches.
Some early-stage tumors can be treated with endoscopic procedures or surgery, while many locally advanced cancers require chemotherapy or chemoradiation before surgery. For selected patients, combined chemotherapy and radiation may be used as the primary treatment without surgery. Advanced or metastatic disease is generally managed with systemic treatment and supportive care tailored to individual needs.
Endoscopic Treatment for Early Esophageal Cancer
Selected very early esophageal cancers that are confined to superficial tissue layers may be treated through endoscopic removal rather than extensive surgery. Procedures such as endoscopic mucosal resection or endoscopic submucosal dissection allow specially trained physicians to remove certain lesions using instruments passed through an endoscope.
Eligibility depends on tumor depth, size, pathological features, and the likelihood of lymph node involvement. Additional treatment or surveillance may be necessary depending on the final findings.
Minimally Invasive and Robot-Assisted Surgery
Surgery to remove part or most of the esophagus, known as esophagectomy, may be recommended for selected patients with localized or locally advanced esophageal cancer. When appropriate, minimally invasive or robot-assisted techniques can be used to perform portions of the operation through smaller incisions.
These approaches may offer recovery advantages for selected patients, although they do not eliminate the risks of major surgery. The choice of procedure depends on the tumor’s location, previous treatment, surgical considerations, and the patient’s overall condition.
Radiation Therapy
Radiation therapy uses focused high-energy radiation to damage cancer cells in a defined treatment area. For many patients with locally advanced esophageal cancer, radiation is combined with chemotherapy before surgery to reduce the tumor burden and improve local disease control.
Definitive chemoradiation may also be recommended for selected patients, particularly those with squamous cell carcinoma or patients who are not appropriate candidates for surgery. Radiation may additionally help relieve symptoms caused by an obstructing or painful tumor.
Chemotherapy
Chemotherapy uses medications that interfere with cancer cell growth. Depending on the diagnosis and treatment plan, chemotherapy may be administered before surgery, before and after surgery, in combination with radiation, or for advanced disease.
For certain patients with resectable esophageal adenocarcinoma, perioperative chemotherapy with regimens such as FLOT may be appropriate. Other patients may receive chemotherapy combined with radiation before surgery. The recommended treatment sequence depends on cancer type, stage, eligibility, and multidisciplinary evaluation.
Immunotherapy
Immunotherapy helps the body’s immune system recognize and attack cancer cells. Immune checkpoint inhibitors may be recommended for selected patients with esophageal or gastroesophageal junction cancer, particularly in advanced disease or certain postoperative settings.
Eligibility may depend on cancer type, stage, previous treatment, and tumor biomarkers, including PD-L1 expression or mismatch repair status. Immunotherapy may be administered alone or with chemotherapy, depending on the clinical circumstances.
Targeted Therapy
Targeted treatments act on specific molecular characteristics or biological pathways involved in cancer growth. For some patients with advanced gastroesophageal junction adenocarcinoma, molecular testing can identify biomarkers such as HER2 or CLDN18.2 that may guide treatment selection.
Targeted medications are not appropriate for every esophageal cancer. Their use depends on the tumor’s specific characteristics, the treatment setting, and available clinical evidence.
Nutrition and Supportive Care
Difficulty swallowing and unintended weight loss are common concerns for patients with esophageal cancer. Nutritional support, symptom management, and coordinated care can be important before, during, and after treatment.
Depending on the patient’s needs, supportive interventions may include nutritional counseling, treatment for pain or reflux, swallowing support, or procedures that help maintain adequate nutrition. The goal is to support quality of life and help patients tolerate appropriate cancer treatment.
Learn More About Esophageal Cancer Treatment
Explore our Stomach and Esophageal Cancer Treatment page to learn more about surgical approaches, chemotherapy, radiation therapy, immunotherapy, and personalized treatment planning.

At Saint John’s Cancer Institute, our multidisciplinary approach brings together specialists in surgical oncology, medical oncology, radiation oncology, gastroenterology, and supportive care to develop individualized treatment plans.
By coordinating clinical expertise, advanced treatment options, and ongoing patient support, we help patients and families navigate complex esophageal and gastroesophageal junction cancers with greater clarity and confidence.
If you have questions about esophageal or stomach cancer, are experiencing concerning symptoms, or would like to discuss an evaluation or second opinion, our team is here to help. Click here to request an appointment.


