
What Is Colorectal Cancer?
Colorectal cancer develops in the colon or rectum, which together form the final portion of the digestive tract. Many colorectal cancers begin as noncancerous growths called polyps that develop in the inner lining of the bowel. Some polyps can gradually acquire abnormal cellular changes and become cancerous over several years. Cancer arising in the colon is called colon cancer, while cancer developing in the rectum is called rectal cancer. Although closely related, these diseases may require different treatment approaches.
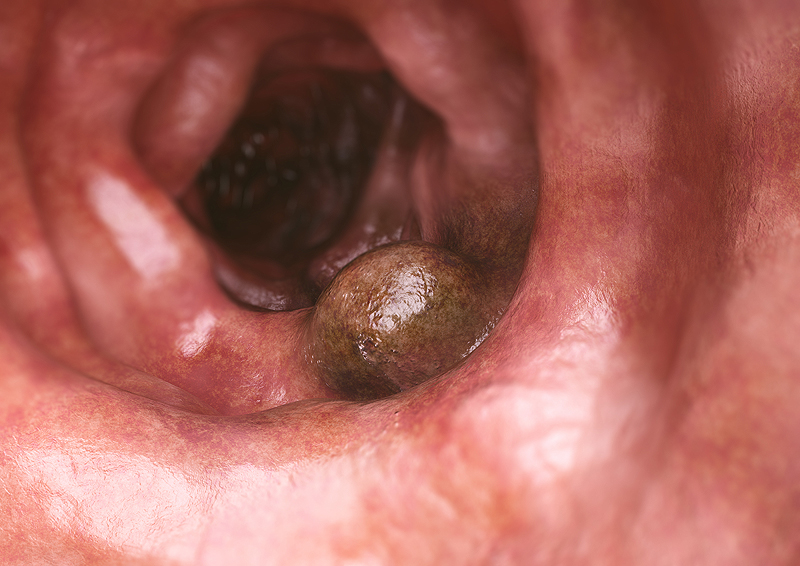
Most colorectal cancers are adenocarcinomas, cancers that develop from gland-forming cells lining the colon or rectum. They generally begin within the innermost lining of the bowel and may grow into deeper layers of its wall. As the cancer advances, cells may spread to nearby lymph nodes or other parts of the body.
Common sites of distant spread include the liver, lungs, and peritoneum, the tissue lining the abdominal cavity. The location of the primary cancer, how deeply it extends into the bowel wall, lymph node involvement, and whether distant metastases are present all contribute to determining the stage.
The colon absorbs water and electrolytes as digestive waste passes through it. The rectum, located at the end of the large intestine, stores stool before a bowel movement. Understanding where a tumor develops helps clinicians select appropriate diagnostic testing, surgery, and additional treatment.
Sections of the Colon
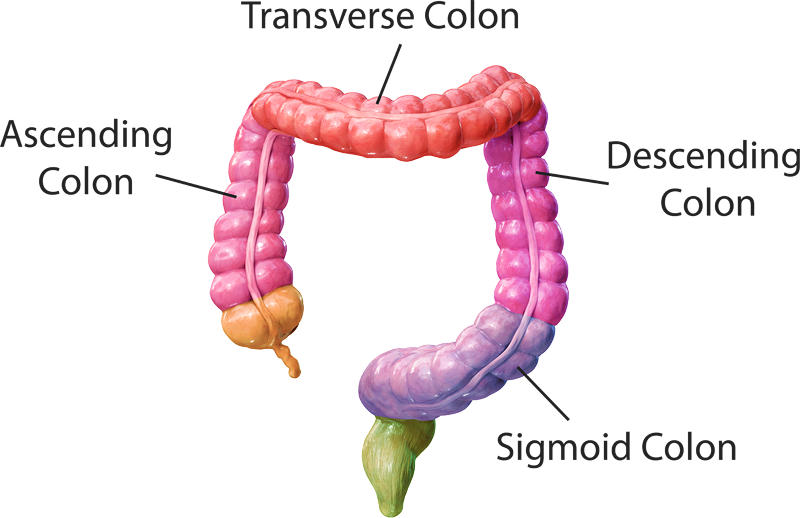
The colon is divided into four principal sections. Each contributes to the movement and processing of digestive waste, and the location of a colorectal tumor can influence the type of surgery and other treatments recommended.
- Ascending Colon: Travels upward along the right side of the abdomen and absorbs water and electrolytes from intestinal contents.
- Transverse Colon: Extends across the upper abdomen and continues the movement and processing of waste.
- Descending Colon: Travels downward along the left side of the abdomen toward the sigmoid colon.
- Sigmoid Colon: The curved final portion of the colon that connects to the rectum.
What Are Colon Polyps, and Are They Cancerous?
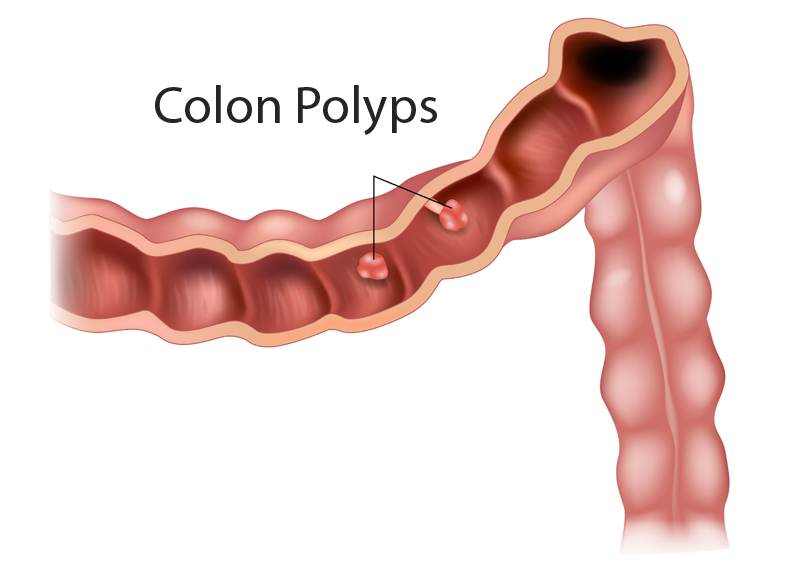
Colon polyps are growths that develop from the inner lining of the colon or rectum. They may be flat, slightly raised, or attached by a stalk. Most polyps are not cancerous when discovered, but certain types can become cancer over time.
Removing precancerous polyps during colonoscopy can prevent some colorectal cancers from developing. A pathologist examines removed tissue to identify the type of polyp and whether abnormal cellular changes are present.
Adenomatous Polyps
Adenomas are considered precancerous because some may develop into colorectal cancer. The likelihood depends on factors such as polyp size, microscopic features, and the degree of dysplasia. Most adenomas do not become cancer, particularly when identified and removed during screening.
Serrated Polyps
Sessile serrated lesions and traditional serrated adenomas are additional types of precancerous colorectal polyps. Some can be difficult to detect because they are flat or have subtle features. Their identification and complete removal are important parts of colorectal cancer prevention.
Hyperplastic and Inflammatory Polyps
Small hyperplastic polyps, particularly those found in the lower colon, are usually low risk. Inflammatory polyps may develop in association with chronic intestinal inflammation and generally are not themselves precancerous. Pathological examination helps distinguish these growths from other polyp types.
Dysplasia
Dysplasia is not a separate type of polyp. It describes abnormal changes in cells that may increase the likelihood of cancer developing. Dysplasia can occur within adenomas, certain serrated lesions, or chronically inflamed intestinal tissue.
People with longstanding inflammatory bowel disease, including ulcerative colitis or Crohn’s colitis, may require specialized surveillance because chronic inflammation can increase colorectal cancer risk.
At Saint John’s Cancer Institute, colorectal cancer care may involve surgical oncologists, medical oncologists, radiation oncologists, gastroenterologists, pathologists, and other specialists. Treatment recommendations consider the tumor’s location, stage, molecular characteristics, and the patient’s overall health. Options may include minimally invasive surgery, systemic therapies, radiation for selected cases, and participation in clinical research when appropriate.
Types of Colorectal Cancers and Tumors
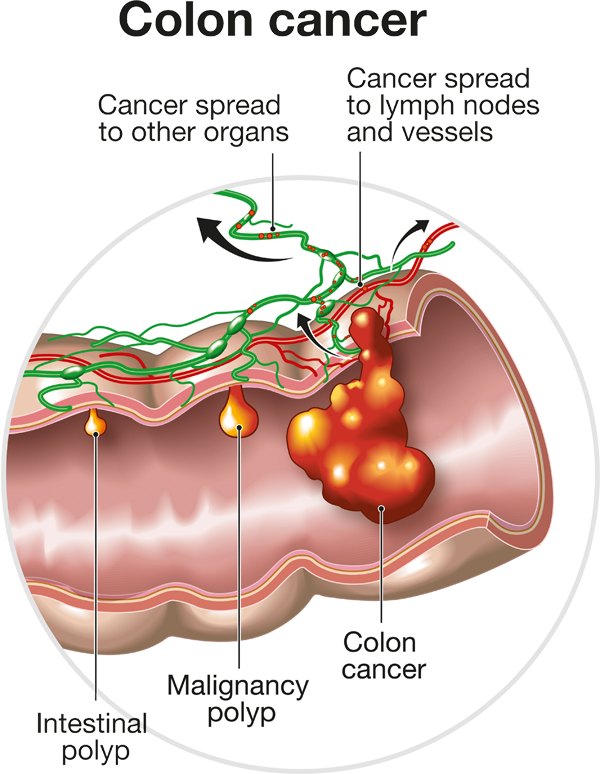
Most colorectal cancers are adenocarcinomas, which develop from gland-forming cells in the lining of the colon or rectum. Less common tumors can originate from neuroendocrine cells, immune system cells, or other tissues within the gastrointestinal tract.
Determining the tumor type and whether the cancer began in the colon or rectum is important because diagnostic testing and treatment can differ. For example, rectal cancer treatment may require particular attention to structures within the pelvis, including nerves involved in bladder, bowel, and sexual function. Modern surgical techniques and individualized treatment planning aim to preserve function whenever possible.
Adenocarcinoma
Adenocarcinoma accounts for the great majority of colorectal cancers. These tumors arise from glandular cells in the inner lining of the colon or rectum. As cancer progresses, it may invade deeper layers of the bowel wall, involve regional lymph nodes, or spread to distant sites such as the liver or lungs.
Neuroendocrine Tumors
Neuroendocrine tumors develop from specialized cells involved in regulating digestive functions. They may occur in the rectum, appendix, small intestine, or other parts of the digestive tract. Their behavior varies according to tumor grade, size, location, and other pathological features. Treatment differs from that used for conventional colorectal adenocarcinoma.
Gastrointestinal Stromal Tumors (GISTs)
Gastrointestinal stromal tumors are uncommon tumors that arise from specialized cells in the wall of the digestive tract, generally related to the interstitial cells of Cajal. They occur most frequently in the stomach or small intestine and only rarely in the colon or rectum.
GISTs are biologically different from colorectal adenocarcinomas. Their potential for aggressive behavior depends on factors such as size, location, mitotic activity, and molecular characteristics. Selected tumors may be treated with surgery or molecularly targeted medications.
Lymphoma
Lymphoma is a cancer of immune system cells that can occasionally involve the colon or rectum. It is classified and treated differently from colorectal adenocarcinoma, with treatment determined by the lymphoma subtype, extent of disease, and individual clinical findings.
Recurrent Colorectal Cancer
Recurrent colorectal cancer refers to cancer that returns after an initial course of treatment. Recurrence may occur near the original tumor site, in regional lymph nodes, or in distant organs. The appropriate treatment depends on the location and extent of recurrence, previous therapies, and whether the disease can be removed or otherwise controlled.
Inherited Colorectal Cancer Syndromes
Most colorectal cancers occur in people without a known inherited cancer syndrome. However, some individuals inherit genetic changes that substantially increase their risk of developing colorectal cancer and, in certain cases, other cancers.
Two important hereditary syndromes are Lynch syndrome and familial adenomatous polyposis (FAP). Both may be inherited in an autosomal dominant pattern, meaning a person with a disease-causing variant can have a 50% chance of passing that variant to each child. Inheriting a variant does not always mean that cancer will develop, and the level of risk depends on the specific syndrome and genetic findings.
Lynch Syndrome (Hereditary Nonpolyposis Colorectal Cancer)
Lynch syndrome is the most common inherited colorectal cancer predisposition syndrome. It generally results from inherited pathogenic variants in genes involved in DNA mismatch repair, including MLH1, MSH2, MSH6, and PMS2, or certain EPCAM alterations that affect MSH2 function.
People with Lynch syndrome have an increased risk of colorectal cancer and may also have increased risks of endometrial, ovarian, stomach, small intestinal, urinary tract, and certain other cancers. Risk varies considerably by gene, age, and other factors.
A diagnosis does not require a particular number of relatives with colorectal cancer. Genetic evaluation may be recommended based on tumor testing, personal or family history, or an identified familial gene variant. Tumor testing for mismatch repair deficiency or microsatellite instability can also inform treatment decisions for patients already diagnosed with colorectal cancer.
When Lynch syndrome is identified, genetic counseling, appropriately timed colonoscopy, and individualized risk-management recommendations can help patients and families make informed decisions.
Familial Adenomatous Polyposis (FAP)
Familial adenomatous polyposis is a rare hereditary condition most commonly associated with pathogenic variants in the APC gene. Classic FAP can cause hundreds or thousands of adenomatous polyps to develop in the colon and rectum, frequently beginning during adolescence or early adulthood.
Without appropriate treatment, classic FAP carries an extremely high lifetime risk of colorectal cancer. Some people have an attenuated form of FAP, involving fewer polyps and a different pattern of cancer risk.
Management may include genetic counseling, colonoscopic surveillance beginning at a younger age, removal of polyps, and preventive surgery when appropriate. Patients may also require evaluation for abnormalities outside the colon, including certain upper gastrointestinal tumors.
Not everyone with FAP has a known family history. Some cases arise from a newly occurring genetic variant. Once a familial variant is identified, genetic testing can help determine which relatives may need specialized surveillance.
Symptoms of Colorectal Cancer
Colorectal cancer often causes no noticeable symptoms in its early stages. When symptoms occur, they are generally similar in women and men, although their nature and severity can vary according to the tumor’s location and extent.
Possible symptoms include:
- Rectal bleeding or blood in the stool
- A persistent change in bowel habits, including diarrhea or constipation
- A change in stool appearance or caliber that persists
- Abdominal pain, cramping, or discomfort
- A recurring sensation of needing to have a bowel movement even after passing stool
- Unexplained weight loss
- Weakness, fatigue, or anemia caused by chronic blood loss
These symptoms can result from conditions other than cancer, including hemorrhoids, infections, or inflammatory bowel disease. However, persistent changes or rectal bleeding should be evaluated by a healthcare professional rather than assumed to be harmless.
Heavy bleeding, severe abdominal pain, or symptoms of a bowel obstruction may require urgent medical attention.
Colorectal Cancer Screening
Screening is important because colorectal cancer and precancerous polyps may develop without symptoms. Screening tests can detect cancer at an earlier stage, and colonoscopy can also prevent certain cancers by identifying and removing precancerous polyps.
The American Cancer Society recommends that adults at average risk begin regular colorectal cancer screening at age 45. Adults in good health with a life expectancy greater than 10 years generally continue screening through age 75. Between ages 76 and 85, decisions should consider overall health, screening history, and preferences. Routine screening is generally not recommended after age 85.
People with a strong family history, previous colorectal cancer or certain polyps, inflammatory bowel disease, hereditary cancer syndromes, or other high-risk conditions may need screening earlier or more frequently.
At-Home Stool Tests
Stool-based screening tests can identify evidence of colorectal cancer or certain advanced precancerous lesions. Different tests look for different markers, including hidden blood, abnormal DNA, or RNA. These tests are generally intended for people without symptoms who are at average risk.
Common options include:
- Fecal Immunochemical Test (FIT): Detects hidden blood in stool and is commonly performed every year.
- High-Sensitivity Guaiac-Based Fecal Occult Blood Test: Uses a chemical method to detect hidden blood and is generally performed annually.
- Multitarget Stool DNA or RNA Testing: Examines selected molecular markers, sometimes combined with blood detection, to identify possible colorectal abnormalities. Recommended testing intervals depend on the particular test.
Stool testing does not remove polyps and cannot identify every cancer or precancerous lesion. An abnormal result requires timely follow-up colonoscopy, even when a patient has no symptoms.
Colonoscopy
Colonoscopy allows a physician to examine the lining of the entire colon and rectum using a flexible instrument with a small camera. Polyps can often be removed during the examination and submitted for pathological evaluation.
For average-risk adults with normal findings, screening colonoscopy is generally performed every 10 years. Patients with previous polyps, relevant family history, or other risk factors may need a different surveillance schedule.
Other Screening Options
CT colonography and flexible sigmoidoscopy are additional screening methods for appropriately selected patients. Newer blood-based screening tests may be considered in some circumstances, although they are less effective at detecting precancerous lesions and certain early-stage cancers than preferred screening approaches.
Choosing a screening method involves discussing personal risk, test effectiveness, preparation, testing intervals, and the need for follow-up if an abnormality is detected.
Screening and diagnostic evaluation are not interchangeable. Patients experiencing persistent symptoms, rectal bleeding, or other concerning changes should discuss appropriate diagnostic testing rather than relying solely on an at-home screening test.
What Are the Risk Factors for Colorectal Cancer?
Several factors may increase the likelihood of developing colorectal cancer. Some, such as age, family history, and inherited genetic changes, cannot be modified. Others are associated with lifestyle or medical conditions that may be addressed through screening, preventive care, and healthier daily habits.
Age
Colorectal cancer becomes more common with increasing age, but it can also occur in younger adults. Because colorectal cancer has been increasing among people younger than 50, current screening recommendations begin at age 45 for adults at average risk.

Personal History of Polyps or Colorectal Cancer
People who have previously had certain precancerous colorectal polyps or colorectal cancer may have an increased risk of developing additional polyps or a new colorectal cancer. Follow-up colonoscopy schedules depend on the type, number, size, and pathological characteristics of previous findings.
Inflammatory Bowel Disease
Longstanding inflammation involving the colon, particularly from ulcerative colitis or Crohn’s colitis, can increase colorectal cancer risk. The level of risk depends on the extent and duration of inflammation and other clinical factors. Specialized surveillance may be recommended.
Family History
Having a parent, sibling, or child with colorectal cancer or certain advanced polyps may increase personal risk. Risk can be greater when a relative was diagnosed at a younger age or several family members have been affected.
Patients with a relevant family history may need to begin colorectal screening earlier than age 45 or undergo colonoscopy more frequently.
Inherited Genetic Conditions
Hereditary conditions such as Lynch syndrome and familial adenomatous polyposis can substantially increase colorectal cancer risk. Genetic counseling and testing may be appropriate for patients whose personal or family history suggests an inherited cancer predisposition.
Some colorectal cancers develop molecular abnormalities that are not inherited. Tumor molecular testing and inherited genetic testing answer different questions, although both may be important in selected patients.
Race, Ethnicity and Health Disparities
Colorectal cancer incidence and mortality vary among population groups. In the United States, Black Americans and some American Indian and Alaska Native populations experience a disproportionate burden of colorectal cancer.
Differences reflect a complex combination of factors, including healthcare access, screening participation, social and environmental conditions, and other influences. Screening and symptom evaluation should be based on individual risk and clinical needs rather than race or ethnicity alone.
Lifestyle and Metabolic Factors
Obesity, physical inactivity, smoking, excessive alcohol consumption, and diets high in processed meat are associated with increased colorectal cancer risk. Type 2 diabetes is also associated with elevated risk in some populations.
Having one or more risk factors does not mean colorectal cancer will develop, and people without recognized risk factors can still be diagnosed. This is why screening remains important.
How Can I Reduce the Risk of Colorectal Cancer?
Not every colorectal cancer can be prevented, but regular screening and certain lifestyle measures can help reduce risk. Screening is particularly valuable because removing precancerous polyps can prevent some cancers from developing.
Risk-reduction strategies include:
- Follow Screening Recommendations: Begin screening at the recommended age or earlier when personal or family history indicates increased risk.
- Maintain Regular Physical Activity: Incorporate consistent activity into daily routines according to individual health and ability.
- Maintain a Healthy Weight: Address excess body weight through sustainable nutrition and physical activity habits.
- Choose a Balanced Diet: Emphasize vegetables, fruit, whole grains, and other fiber-containing foods while limiting processed meat and excessive red meat consumption.
- Avoid Tobacco: Smoking is associated with increased colorectal cancer risk as well as many other health complications.
- Limit Alcohol: Reducing alcohol consumption can help lower cancer risk; avoiding alcohol provides the greatest reduction in alcohol-related cancer exposure.
- Discuss Family History: Inform your healthcare team about relatives with colorectal cancer, advanced polyps, or relevant hereditary syndromes.
Aspirin and Other Medications
Some studies suggest that aspirin may reduce colorectal cancer risk in particular populations, including certain people with Lynch syndrome. However, aspirin and other nonsteroidal anti-inflammatory medications can cause significant bleeding and other complications and are not routinely recommended solely to prevent colorectal cancer in average-risk adults.
Patients should not begin aspirin or other medications for colorectal cancer prevention without discussing their individual risks and possible benefits with a healthcare professional.
Hormone replacement therapy is not recommended as a strategy to prevent colorectal cancer because its overall risks and benefits depend on other medical considerations.
Diagnosing Colorectal Cancer
When colorectal cancer is suspected, diagnostic evaluation is used to confirm the presence of cancer and determine its location and extent. The process may involve colonoscopy with biopsy, laboratory testing, imaging, and examination of tissue obtained during a procedure.
Screening tests are generally used in people without symptoms. Diagnostic tests are used when symptoms, an abnormal screening result, or another clinical finding requires investigation.
Colonoscopy and Tissue Biopsy
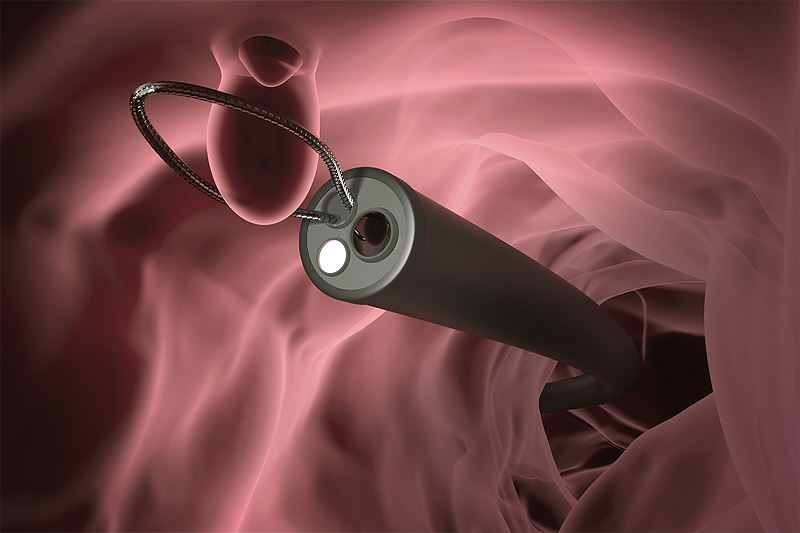
Colonoscopy is a principal method for evaluating suspected colorectal cancer. A flexible instrument equipped with a camera is passed through the rectum to examine the lining of the colon. Suspicious abnormalities can be biopsied, and many polyps can be removed during the procedure.
A pathologist examines collected tissue to determine whether cancer is present, identify the tumor type, and assess other relevant microscopic features.
Flexible Sigmoidoscopy
Flexible sigmoidoscopy examines the rectum and lower part of the colon. It may be appropriate for selected symptoms or screening situations, but does not evaluate the entire colon. Additional colonoscopy may be necessary depending on the findings.
Blood Tests and Carcinoembryonic Antigen (CEA)
Blood tests may help identify anemia, evaluate liver function, and assess the patient’s overall health. Carcinoembryonic antigen (CEA) is a tumor marker that may be elevated in some people with colorectal cancer.
CEA is not reliable enough to diagnose colorectal cancer or serve as a routine screening test by itself. It may be useful for establishing a baseline before treatment and monitoring selected patients after treatment.
CT Imaging
Computed tomography (CT) uses X-rays and computerized reconstruction to create detailed cross-sectional images of the body. CT scans of the chest, abdomen, and pelvis are commonly used in staging colorectal cancer and identifying possible spread to distant organs.
Magnetic Resonance Imaging (MRI)
MRI uses magnetic fields and radio waves to create detailed images. Pelvic MRI is particularly important in staging rectal cancer because it helps assess how deeply a tumor extends, its relationship to nearby structures, and other findings that influence treatment planning.
Liver MRI may also be useful when additional characterization of suspected liver metastases is needed.
Endoscopic Ultrasound
Endoscopic ultrasound uses high-frequency sound waves from a probe placed near the rectal wall. It may be used to assess selected rectal tumors, particularly certain early lesions. Pelvic MRI is generally preferred for comprehensive local staging of many rectal cancers.
PET/CT and Other Imaging
PET/CT combines anatomical imaging with information about the metabolic activity of tissues. It is not routinely necessary for every newly diagnosed colorectal cancer, but may be considered when conventional imaging leaves important questions unresolved or when results could change treatment decisions.
CT Colonography
CT colonography, sometimes called virtual colonoscopy, uses CT imaging to examine the colon for polyps or other abnormalities. It can be an appropriate screening option in selected patients but does not allow tissue biopsy or polyp removal during the examination.
When CT colonography identifies a suspicious lesion, conventional colonoscopy is generally needed for further evaluation or removal.
Molecular and Genetic Testing
Colorectal tumors may undergo testing for mismatch repair deficiency or microsatellite instability, which can help identify possible Lynch syndrome and guide treatment decisions. In advanced disease, testing for alterations such as RAS, BRAF, and other relevant biomarkers may determine eligibility for particular targeted or immune-based therapies.
Tumor testing does not necessarily establish an inherited cancer syndrome. Genetic counseling and germline testing may be recommended when inherited risk is suspected.
Colorectal Cancer Stages
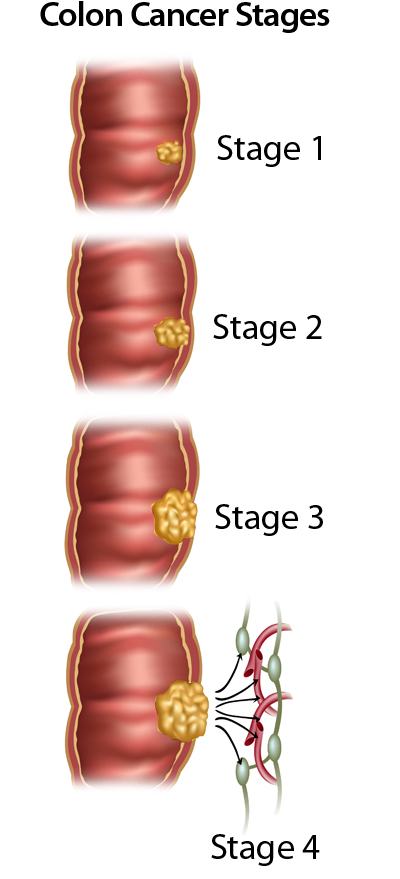
Staging describes how extensively colorectal cancer has grown and whether it has spread to lymph nodes or other parts of the body. Most colorectal cancers are staged using the TNM system, which considers the primary tumor (T), regional lymph nodes (N), and distant metastases (M).
The stage helps clinicians determine the appropriate treatment and estimate prognosis. Clinical stage is based on examinations and testing before treatment, while pathological stage may incorporate findings from surgically removed tissue. Treatment given before surgery can also affect how subsequent staging is recorded.
Stage 0 — Carcinoma in Situ
Abnormal cancerous cells are confined to the innermost lining of the colon or rectum and have not invaded deeper layers. Depending on the size and location, removal during an endoscopic procedure or local surgery may be appropriate.
Stage I
Cancer has grown into the submucosa or muscular layer of the bowel wall but has not spread to regional lymph nodes or distant organs. Surgery is a common treatment, although the exact approach differs according to whether the tumor is in the colon or rectum.
Stage II
Cancer has grown through deeper layers of the colon or rectal wall, and may extend into nearby tissues or structures, but regional lymph node metastases have not been identified. The stage is subdivided into IIA, IIB, and IIC according to the extent of local tumor invasion.
Stage III
Cancer has spread to regional lymph nodes or meets certain other regional tumor-deposit criteria, but distant metastases have not been identified. Substages IIIA, IIIB, and IIIC depend on combinations of tumor invasion and regional disease findings.
Stage IV
Cancer has spread to distant organs or tissues, such as the liver, lungs, or peritoneum. Stage IV is divided into IVA, IVB, and IVC according to the pattern and extent of distant spread.
Even when colorectal cancer is advanced, treatment may help control the disease, relieve symptoms, and, in carefully selected cases with limited metastases, offer an opportunity for long-term disease control or potentially curative treatment.
Colorectal Cancer Treatment Summary
Treatment for colorectal cancer depends on whether the tumor is located in the colon or rectum, the stage of disease, molecular characteristics, and the patient’s overall health. Care may involve collaboration among surgical oncologists, medical oncologists, radiation oncologists, gastroenterologists, pathologists, and other specialists.
Many localized colon cancers are treated primarily with surgery, while selected rectal cancers may benefit from chemotherapy, radiation, or immunotherapy before surgery. Advanced colorectal cancer may require systemic therapy, surgery for selected metastatic tumors, or other individualized approaches.
Minimally Invasive and Robotic Surgery
Surgery is an important treatment for many patients with localized colorectal cancer. Depending on the tumor and patient characteristics, a minimally invasive laparoscopic or robotic-assisted approach may be appropriate. These techniques use smaller incisions and may reduce some aspects of postoperative recovery compared with open surgery.
Not every patient is a candidate for minimally invasive surgery. The procedure must allow appropriate cancer removal, lymph node evaluation, and preservation of surrounding structures when feasible.
Chemotherapy
Chemotherapy uses medications that interfere with cancer cell growth and division. It may be recommended after surgery for certain higher-risk colon cancers, before or after surgery for selected rectal cancers, or as treatment for advanced disease.
Treatment regimens vary according to disease stage, previous treatment, molecular findings, and anticipated benefits and risks.

Radiation Therapy
Radiation therapy uses directed high-energy radiation to treat cancer within a specific area. It is commonly incorporated into treatment for selected patients with rectal cancer, particularly when local tumor control is important.
Radiation is not routinely recommended after surgery for most colon cancers but may be considered in special circumstances or to relieve symptoms from particular tumors.
Immunotherapy
Immune checkpoint inhibitors may be particularly effective for colorectal cancers with deficient mismatch repair (dMMR) or high microsatellite instability (MSI-H). Testing for these tumor characteristics helps identify patients who may benefit.
Immunotherapy is an established option for selected patients with advanced colorectal cancer and may also play a role in treating certain locally advanced rectal cancers. Its use depends on tumor biomarkers, disease stage, treatment goals, and the individual clinical situation.
Targeted Therapy
Targeted treatments interfere with molecular pathways or signals that help colorectal cancer cells grow. Depending on the tumor’s characteristics, treatments may involve medications directed toward EGFR, VEGF, BRAF, or other relevant pathways.
Molecular testing can help determine which treatments may be appropriate. These medications are not interchangeable, and some require particular biomarkers or previous treatments.
Treatment of Selected Metastatic Disease
For some patients whose colorectal cancer has spread to a limited number of sites, particularly in the liver or lungs, surgery or other local treatments may be considered. Options can include removal of metastatic tumors, ablation, or carefully selected radiation approaches, sometimes in combination with systemic therapy.
These decisions depend on the extent of disease, whether all known tumor sites can be treated, and the patient’s overall clinical circumstances.
Learn More About Colorectal Cancer Treatment
Explore our Colorectal Cancer Treatment page for additional information about surgery, systemic therapies, radiation, and individualized treatment planning.
If you have received a colorectal cancer diagnosis, are experiencing concerning symptoms, or would like to understand your treatment options, our multidisciplinary team can help you take the next step. Contact Saint John’s Health Center to learn more about evaluation, treatment planning, and available clinical resources.
If you have questions regarding Colorectal Cancers, please call today. Click here to request an appointment.



