
Breast cancer surgery is planned according to the type and extent of the cancer, the size and shape of the breast, lymph node findings, other treatments that may be needed and each patient’s goals and preferences. At the Margie Petersen Breast Center, fellowship-trained breast surgeons work with medical oncologists, radiation oncologists, breast imaging specialists, and pathologists to determine the surgical approach that is most appropriate for each patient.
Surgical options may include breast-conserving surgery, oncoplastic techniques, mastectomy, sentinel lymph node biopsy and breast reconstruction. The goal is to remove the cancer effectively while considering breast appearance, function, recovery and the treatments that may follow surgery.
Breast-Conserving Surgery (Lumpectomy or Partial Mastectomy)

Breast-conserving surgery, also called lumpectomy or partial mastectomy, removes the cancer along with a margin of surrounding breast tissue while preserving the remainder of the breast. It can be an appropriate option for many patients with ductal carcinoma in situ (DCIS) or invasive breast cancer when the cancer can be removed with clear margins and an acceptable breast appearance.
Whether breast-conserving surgery is appropriate depends on several factors, including the size of the cancer relative to the breast, the number and location of areas involved, previous treatments and whether radiation therapy can be safely given. Most patients who undergo breast-conserving surgery receive radiation therapy afterward, although recommendations are individualized.
For appropriately selected patients, breast-conserving surgery followed by radiation provides survival outcomes equivalent to mastectomy. The amount of breast tissue removed, incision placement and resulting breast shape vary according to the location and extent of the cancer and the surgical technique used.
Oncoplastic Surgery
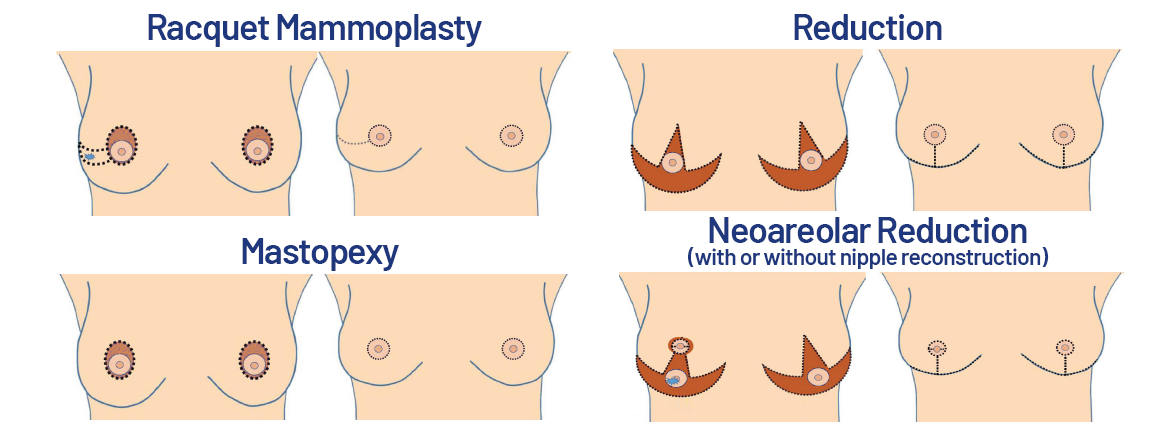
Oncoplastic surgery combines cancer removal with breast reshaping techniques during the same operation. By rearranging the remaining breast tissue after a lumpectomy or partial mastectomy, the surgeon may be able to remove a larger area of tissue while preserving the overall contour of the breast.
This approach can be particularly useful when the cancer is relatively large compared with the breast, is located in an area where a standard lumpectomy could noticeably change breast shape, or when breast reduction or lifting techniques may help achieve symmetry. In selected patients, oncoplastic surgery can expand the possibility of breast conservation when mastectomy might otherwise have been considered.
Some procedures involve surgery on the opposite breast to improve symmetry. The specific approach depends on the cancer location, breast anatomy, amount of tissue that must be removed and the patient’s preferences.
Mastectomy
Mastectomy removes the breast when breast-conserving surgery is not appropriate or when mastectomy is preferred after discussion of the available options. It may be recommended because of the size or location of the cancer, involvement of multiple areas of the breast, previous radiation treatment, certain inherited cancer risks or other clinical factors.
Mastectomy substantially reduces the amount of breast tissue but does not eliminate every breast cell or completely eliminate the possibility of cancer returning in the chest wall or nearby tissues. Many patients do not require radiation therapy after mastectomy, although radiation may still be recommended depending on the size and characteristics of the cancer, lymph node involvement and other pathologic findings.
Types of Mastectomy
The type of mastectomy recommended depends on the cancer, breast anatomy, whether reconstruction is planned and whether the skin or nipple can safely be preserved.
Total Mastectomy

A total, or simple, mastectomy removes the breast tissue, nipple and areola and a portion of the overlying skin. It may be performed when breast conservation is not appropriate or when a patient chooses mastectomy after discussing the available surgical options. Reconstruction may be performed at the same operation or at a later time, or a patient may choose not to undergo reconstruction.
Skin-Sparing Mastectomy
A skin-sparing mastectomy removes the breast tissue, nipple and areola while preserving most of the breast skin. Preserving the skin envelope can facilitate immediate breast reconstruction and help the surgical oncologist who specializes oncoplastic surgery recreate the breast contour.
Nipple-Sparing Mastectomy
A nipple-sparing mastectomy removes the underlying breast tissue while preserving the breast skin, nipple and areola. It may be an option for selected patients when the location and characteristics of the cancer allow the nipple and surrounding tissue to be safely preserved. Sensation in the nipple and breast commonly changes after surgery and may be significantly reduced or lost.
Modified Radical Mastectomy
A modified radical mastectomy combines removal of the breast with an axillary lymph node dissection while preserving the chest muscles. It may be recommended when more extensive lymph node surgery is required. Reconstruction may be performed at the time of mastectomy or later depending on the treatment plan.
Oncoplastic Breast Surgery – A Novel Approach to Breast Cancer Surgery Webinar
Learn more about how oncoplastic breast surgery can combine cancer removal with breast reshaping techniques.
Breast Reconstruction
Breast reconstruction can restore the shape and contour of the breast after mastectomy and, in some situations, after breast-conserving surgery. Reconstruction may begin during the same operation as the breast cancer surgery or may be performed later, after healing or other treatments have been completed.
Not every patient chooses breast reconstruction. Some patients prefer a flat closure or may decide to consider reconstruction at a later time. When reconstruction is desired, the approach is individualized according to breast anatomy, the cancer treatment plan, previous surgery or radiation, overall health and the patient’s preferences.
Implant-Based Reconstruction
Implant-based reconstruction uses a saline- or silicone-filled breast implant to recreate the breast shape. In some patients, an implant can be placed at the time of mastectomy. In others, a temporary tissue expander is placed first and gradually adjusted before being replaced with a permanent implant.
Implant reconstruction generally involves a shorter operation and recovery than reconstruction using tissue from another part of the body. However, implants are not lifetime devices, and additional procedures may be needed over time because of changes in the implant, scar tissue surrounding it, breast appearance or other complications.
Reconstruction Using Your Own Tissue
Autologous reconstruction uses skin, fat and sometimes muscle from another part of the body to create the breast mound. Tissue may be taken from areas such as the abdomen, back, thigh or buttock, depending on the patient’s anatomy and the reconstructive technique being used.
Because this type of reconstruction uses the patient’s own tissue, it can provide a breast that changes naturally with the body over time. The surgery is generally more complex than implant reconstruction and may involve a longer initial recovery as well as healing at the site where the tissue was taken.
When Is Breast Reconstruction Performed?
Reconstruction may be immediate, beginning at the time of mastectomy, or delayed until after the breast has healed and other cancer treatment has been completed. The anticipated need for radiation therapy can influence the timing and type of reconstruction, so reconstructive planning is ideally coordinated with the breast surgeon, plastic surgeon, medical oncologist and radiation oncologist when appropriate.
Some patients also undergo procedures on the opposite breast to improve symmetry. Reconstruction decisions are highly individual, and there is no single approach that is right for every patient.
Lymph Node Surgery
Breast cancer can spread through lymphatic channels to nearby lymph nodes, most commonly those in the underarm, or axilla. Evaluating these nodes can provide important staging information and help determine whether additional treatment is needed.
Not every patient requires the same amount of lymph node surgery. The approach depends on whether the cancer is invasive, whether lymph nodes appear abnormal before surgery, results of imaging or needle biopsy, the type of breast surgery being performed and other features of the cancer.
Sentinel Lymph Node Biopsy
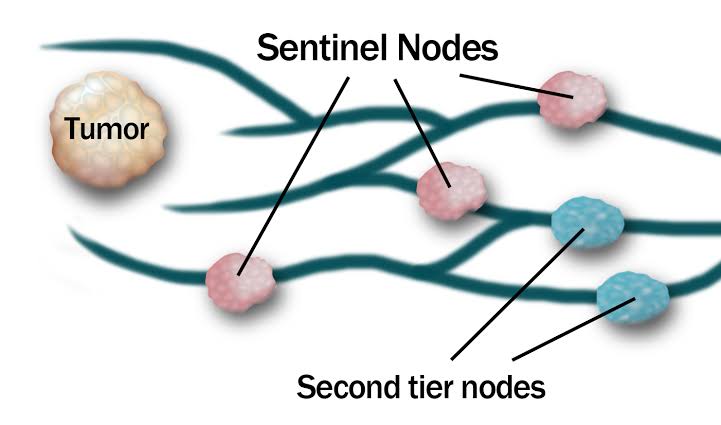
A sentinel lymph node biopsy identifies and removes the first lymph node or small group of lymph nodes most likely to receive drainage from the breast. These nodes are examined by a pathologist for evidence of cancer.
Because only selected lymph nodes are removed, sentinel node biopsy causes less disruption of the lymphatic system than a full axillary dissection and is associated with a lower risk of complications such as arm swelling and shoulder stiffness. It may be performed at the same time as lumpectomy or mastectomy.
Axillary Lymph Node Dissection
An axillary lymph node dissection removes a larger group of lymph nodes and surrounding tissue from the underarm. It may be recommended when the extent of lymph node involvement or other clinical findings indicate that more extensive axillary treatment is needed.
Not every patient with cancer found in a lymph node requires an axillary dissection. Advances in breast surgery, radiation therapy and systemic treatment have allowed some patients with limited lymph node involvement to safely avoid more extensive lymph node surgery. The decision depends on the amount of nodal disease, the breast operation being performed, planned radiation therapy and other characteristics of the cancer.
Lymphedema After Breast Cancer Treatment
Lymphedema is swelling caused by a buildup of lymphatic fluid when normal lymph drainage has been disrupted. After breast cancer treatment, it can affect the arm, hand, breast or chest wall on the treated side and may develop soon after treatment or months to years later.
The risk of lymphedema generally increases when more lymph nodes are removed and when lymph node surgery is combined with radiation to regional lymph nodes. Most patients do not develop severe lymphedema, but recognizing early changes can allow treatment to begin before swelling becomes more difficult to manage.
Signs to Report
Patients should let their care team know about new or persistent swelling, heaviness, tightness, aching or changes in the fit of clothing, jewelry or sleeves on the treated side. Changes involving the breast or chest wall should also be evaluated.
Lymphedema Treatment and Rehabilitation
Providence Saint John’s Health Center includes physical therapists trained in the evaluation and treatment of lymphedema. Management may include specialized exercise, compression, manual lymphatic techniques, skin care and other strategies selected according to the location and severity of the swelling.
Physical therapy can also help patients restore shoulder mobility, strength and function after breast and lymph node surgery.
Frequently Asked Questions About Breast Cancer Surgery
What are the potential side effects of breast cancer surgery?
Side effects depend on the type and extent of surgery. Common short-term effects can include pain or soreness, swelling, bruising, fatigue, temporary limitations in shoulder or arm movement and fluid buildup near the surgical site. Infection, bleeding and wound-healing problems can also occur.
Some patients experience longer-term changes such as numbness or altered sensation in the breast, chest wall or underarm. Lymphedema is another possible complication when lymph nodes are removed or treated. Reconstruction can have additional risks depending on whether implants or the patient’s own tissue are used.
How long will it take to recover from breast cancer surgery?
Recovery time varies according to the procedure and the individual patient. Many patients recover relatively quickly after lumpectomy, while mastectomy generally requires a longer recovery. Surgery that includes breast reconstruction may require several additional weeks, particularly when tissue is transferred from another part of the body.
Your surgical team will give you individualized guidance about wound care, drains when necessary, driving, lifting, exercise and returning to work. Recovery should be based on healing and the type of surgery performed rather than a single timetable for every patient.
Will I need additional treatment after surgery?
Many patients receive additional treatment before or after breast surgery. Recommendations depend on the type and stage of breast cancer, lymph node findings, tumor grade, hormone receptor and HER2 status and other characteristics of the cancer.
Treatment may include radiation therapy, endocrine therapy, chemotherapy, HER2-targeted therapy or other systemic treatments. In some situations, medication is given before surgery rather than afterward. The breast surgeon, medical oncologist and radiation oncologist coordinate these recommendations as part of the overall treatment plan.
What are my options for breast reconstruction, and when can it be done?
Breast reconstruction may use implants, the patient’s own tissue or a combination of techniques. It can sometimes begin at the time of mastectomy or be delayed until after recovery and other cancer treatment. Some patients choose not to undergo reconstruction and may prefer an aesthetic flat closure or an external breast prosthesis.
The timing and type of reconstruction depend on the breast surgery, whether radiation therapy may be needed, previous treatment, overall health, anatomy and personal preferences. Discussing reconstruction before mastectomy can help patients understand the full range of options even when reconstruction will be performed later.
How will breast cancer surgery affect my daily activities?
Most patients can gradually resume normal activities as healing progresses, but temporary restrictions are common. Depending on the operation, patients may need to limit heavy lifting, strenuous exercise and certain arm movements while incisions heal. Patients undergoing more extensive surgery or reconstruction may need additional help at home during the early recovery period.
Exercises and physical therapy may be recommended to restore shoulder movement, strength and function. Your care team will provide instructions based on the operation and should be contacted if you develop increasing pain, swelling, redness, drainage, fever or other concerning changes during recovery.
We Are Ready to Support You

Choosing breast cancer surgery involves more than selecting a procedure. It means understanding what each option can accomplish, how it fits with the rest of your treatment and what the decision may mean for recovery, breast appearance and daily life.
At the Margie Petersen Breast Center, our breast surgeons and multidisciplinary specialists work with you to review the clinical findings, explain the available surgical options and develop a treatment plan that reflects both the cancer and your individual priorities.
Talk With Our Breast Clinic Team
The Breast Health Clinic can be reached at (310) 582-7209. If you have questions about a new breast symptom, need an evaluation or would like help determining your next step, call and a member of our team can assist you.







