
Bladder cancer affects more than 84,000 people in the United States each year and occurs substantially more often in men than women. At Providence Saint John’s Cancer Institute, patients receive coordinated care from specialists across urologic oncology, medical oncology, radiation oncology and other disciplines, with treatment personalized to the type and stage of cancer and each patient’s individual needs.
What Is Bladder Cancer?
Bladder cancer begins when abnormal cells grow within the bladder. Most bladder cancers develop in the urothelial cells that line the inside of the bladder and are called urothelial carcinomas. Some remain within the inner layers of the bladder, while others grow into the bladder muscle or surrounding tissues and, in more advanced disease, may spread to lymph nodes or other parts of the body.
What Are the Signs and Symptoms of Bladder Cancer?
Blood in the urine, also called hematuria, is one of the most common signs of bladder cancer. Urine may appear pink, red or brown, although sometimes blood is found only during a urine test. Other symptoms may include:
- Feeling an urgent need to urinate
- Urinating more frequently than usual
- Feeling the need to urinate even when the bladder is not full
- Difficulty urinating or a weak urine stream
- Pain or burning during urination
These symptoms can also be caused by urinary tract infections, an enlarged prostate, bladder stones and other conditions. Blood in the urine or persistent changes in urination should be evaluated to determine the cause.
What Increases the Risk of Bladder Cancer?
Bladder cancer can occur without an identifiable cause, but several factors are associated with increased risk. Smoking is the leading preventable risk factor, and risk generally increases with the amount and duration of tobacco exposure.
- Smoking or a history of tobacco use
- Increasing age
- Being male
- Long-term workplace exposure to certain industrial chemicals
- Previous treatment with certain cancer medications or radiation to the pelvis
- Chronic bladder irritation in some patients
- A personal history of bladder or other urothelial cancer
Occupational risk has been associated with long-term exposure to certain chemicals used in industries such as dye, rubber, leather, textiles, metal manufacturing and painting. Having a risk factor does not mean that a person will develop bladder cancer, but understanding individual risk can help guide evaluation when symptoms occur.
Understanding Bladder Cancer Stage
If bladder cancer is diagnosed, the next step is determining how deeply it has grown and whether it has spread beyond the bladder. Stage, tumor grade and other characteristics help determine the risk of recurrence or progression and guide treatment. One of the most important distinctions is whether cancer has reached the muscular wall of the bladder.
Non-Muscle-Invasive Bladder Cancer (NMIBC)
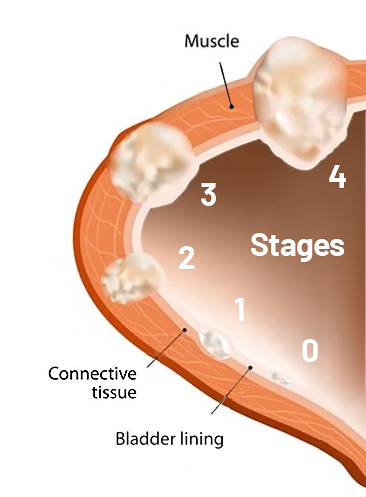
Non-muscle-invasive bladder cancer is confined to the inner lining of the bladder or the connective tissue beneath it and has not grown into the bladder muscle. This includes Stage 0 and Stage I cancers. Because these tumors can differ substantially in their likelihood of returning or progressing, they are also classified according to factors such as grade and recurrence risk.
Muscle-Invasive Bladder Cancer (MIBC)
Muscle-invasive bladder cancer has grown into the muscular wall of the bladder. These cancers require a more intensive treatment strategy and may be treated with radical cystectomy and systemic therapy or, for appropriately selected patients, a bladder-preserving approach combining TURBT, chemotherapy and radiation therapy.
Locally Advanced or Metastatic Bladder Cancer
More advanced bladder cancer may grow through the bladder wall into nearby tissues or organs, involve lymph nodes, or spread to distant areas of the body. Treatment increasingly relies on coordinated systemic therapy and may include chemotherapy, immunotherapy, antibody-drug conjugates, targeted therapy, radiation therapy and clinical trials depending on the individual cancer and previous treatment.
How Is Bladder Cancer Treated?

Bladder cancer treatment depends on whether the cancer is non-muscle-invasive, muscle-invasive or more advanced, as well as tumor grade, overall health and personal treatment goals. Options may include TURBT, intravesical therapy, surgery, chemotherapy, immunotherapy, radiation therapy and other systemic treatments. Because several specialties may contribute to care, treatment planning at Saint John’s brings together the expertise needed to develop an individualized approach.
Treatment for Non-Muscle-Invasive Bladder Cancer
For many patients with non-muscle-invasive bladder cancer, treatment begins with TURBT to remove visible tumor and obtain tissue for detailed analysis. Depending on the tumor’s grade and risk of recurrence or progression, treatment may then include careful surveillance or medication delivered directly into the bladder.
Intravesical Therapy and BCG
Intravesical therapy delivers medication directly into the bladder through a catheter, allowing treatment to come into contact with the bladder lining while limiting exposure elsewhere in the body. Depending on the cancer’s risk characteristics, intravesical chemotherapy or immunotherapy may be recommended after TURBT.
Bacillus Calmette-Guérin (BCG) is an intravesical immunotherapy commonly used for certain intermediate- and high-risk non-muscle-invasive bladder cancers. BCG stimulates an immune response within the bladder to attack cancer cells and reduce the likelihood that the cancer will return or progress.
For some high-risk bladder cancers that persist or return despite BCG, additional intravesical treatments, systemic immunotherapy, clinical trials or bladder removal may be considered. Treatment is individualized according to the characteristics of the cancer, previous therapy and the patient’s overall goals.
Bladder-Preserving Therapy for Muscle-Invasive Bladder Cancer
For appropriately selected patients with muscle-invasive bladder cancer, treatment may sometimes be designed to preserve the bladder rather than remove it. This approach, known as trimodal therapy, combines maximal removal of the bladder tumor through TURBT with chemotherapy and radiation therapy. Careful evaluation and follow-up are essential because bladder preservation is not appropriate for every tumor or every patient.
Preserving the Bladder When Appropriate
Can the bladder be preserved with muscle-invasive bladder cancer?
Radical cystectomy remains an important treatment for muscle-invasive bladder cancer, but selected patients may be candidates for bladder-preserving trimodal therapy.
In this video, Jennifer Linehan, MD, a urologic oncologist, explains how the gold-standard of bladder cancer treatment has changed, moving away from cystectomy and offering greater options for patients. The process involves a combined treatment approach which has been demonstrated to provide favorable results. She further discusses how careful patient selection and coordinated treatment can provide another potentially curative approach for some patients.
Watch this video on bladder-sparing therapy with Dr. Jennifer Linehan and learn who may qualify for this medical technique.
Surgery for Bladder Cancer
Surgery plays an important role in both early and muscle-invasive bladder cancer. The appropriate procedure depends on how deeply the cancer has grown, its location and extent, previous treatment, overall health and whether bladder preservation is appropriate.
Transurethral Resection of Bladder Tumor (TURBT)
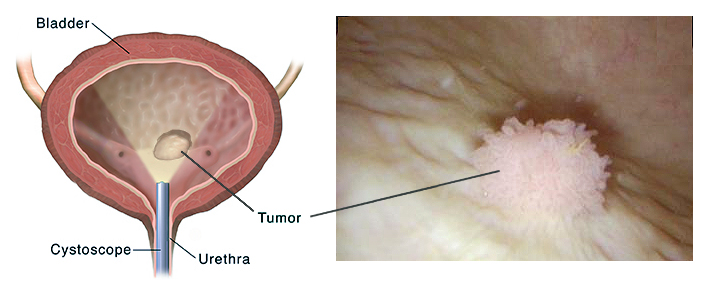
TURBT removes bladder tumors through the urethra using a cystoscope, without an external incision. It is central to the diagnosis and treatment of non-muscle-invasive bladder cancer and may also be used as part of a bladder-preserving treatment strategy for selected muscle-invasive cancers.
Radical Cystectomy
When bladder cancer has invaded the muscle or has other high-risk characteristics, removal of the bladder may provide the most appropriate cancer treatment. Radical cystectomy removes the bladder along with nearby lymph nodes and other surrounding structures as appropriate. A new pathway for storing and eliminating urine is then created through urinary reconstruction or diversion.
Robotic-Assisted Cystectomy
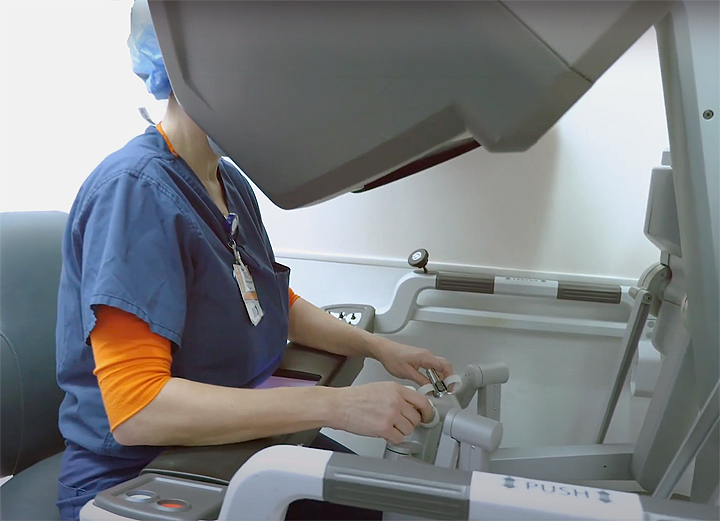
For appropriately selected patients, radical cystectomy may be performed using a robotic-assisted minimally invasive approach. The surgeon controls specialized instruments through small abdominal incisions, providing precise access for removal of the bladder and lymph nodes while planning urinary reconstruction according to the individual patient’s needs.
Systemic Treatment for Bladder Cancer
Systemic treatments travel through the bloodstream and can treat cancer cells throughout the body. They may be used before or after surgery for muscle-invasive bladder cancer or as primary treatment when cancer has spread beyond the bladder. The appropriate therapy depends on the stage of disease, previous treatment, overall health and the biological characteristics of the cancer.
Chemotherapy
Chemotherapy remains an important component of bladder cancer treatment. For eligible patients with muscle-invasive disease, chemotherapy may be given before radical cystectomy to treat cancer cells that may have moved beyond the bladder and improve the effectiveness of the overall treatment strategy. Chemotherapy may also be used as part of bladder-preserving chemoradiation or in the treatment of advanced disease.
Immunotherapy and Advanced Systemic Treatments
Immunotherapy helps the immune system recognize and attack cancer cells and may be used in several bladder cancer settings. For advanced or metastatic urothelial cancer, treatment has expanded to include immunotherapy, antibody-drug conjugates and targeted therapies for selected cancers with specific genetic and molecular changes. These advances make individualized treatment planning and access to clinical research increasingly important.
Clinical Trials and Research
Clinical trials may provide access to promising treatment strategies while helping researchers improve care for future patients. At Saint John’s Cancer Institute, clinical and translational research complement multidisciplinary cancer care, allowing new discoveries to be evaluated and translated into more personalized approaches to bladder cancer treatment.
If you have questions regarding bladder cancer treatment, please call today. Click here to request an appointment.
More from Our Blog





Providence St. John’s Health Center
High Performing in Urology
Saint John’s Health Center is nationally ranked and in the top 10% for Urology
Learn more at Health.USNews.com.