
Prostate cancer can behave very differently from one person to another. Some prostate cancers grow slowly and can be safely monitored, while others require treatment because they are more likely to grow or spread. At Providence Saint John’s Health Center and Saint John’s Cancer Institute, our specialists evaluate each patient’s cancer, overall health and treatment goals to develop a personalized approach to care.
What Is Prostate Cancer?
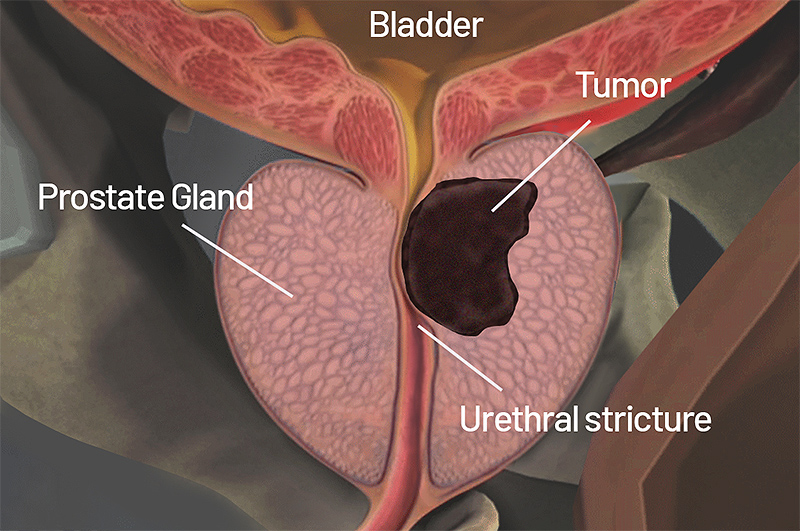
The prostate is a small gland located below the bladder and in front of the rectum. It surrounds part of the urethra, the tube that carries urine out of the body, and produces fluid that contributes to semen. Prostate cancer develops when cells within the gland begin growing abnormally and continue dividing when they should not.
How Does Prostate Cancer Behave?
Many prostate cancers grow slowly and remain confined to the prostate for years. These cancers may have a low risk of causing harm and can sometimes be monitored rather than treated immediately. Other prostate cancers have biological features that make them more likely to grow, extend beyond the prostate or spread to other parts of the body.
Understanding how a particular prostate cancer is likely to behave is therefore an important part of treatment planning. PSA level, biopsy findings, Grade Group, tumor extent, imaging and other clinical factors can help determine whether monitoring or treatment is appropriate.
What Are the Signs and Symptoms of Prostate Cancer?

Early prostate cancer often causes no noticeable symptoms. When symptoms occur, particularly with more advanced disease, they can vary according to the location and extent of the cancer.
- Difficulty starting or maintaining urination
- Weak or interrupted urine flow
- Increased urinary frequency, particularly at night
- Blood in the urine or semen
- Erectile dysfunction
- Persistent pain in the back, hips or other bones when cancer has spread to bone
- Unexplained weight loss or fatigue with more advanced disease
Do Urinary Symptoms Mean I Have Prostate Cancer?
No. Urinary frequency, urgency, a weak stream and difficulty emptying the bladder are commonly caused by noncancerous conditions, particularly benign prostatic hyperplasia (BPH), or an enlarged prostate. Because prostate cancer may produce no symptoms in its early stages, symptoms alone cannot determine whether cancer is present.
You can learn more about how benign prostatic hyperplasia (BPH) affects urination and how an enlarged prostate is evaluated and treated.
Finding clinically significant prostate cancer while it is still localized can provide more opportunities for effective treatment.
What Increases the Risk of Prostate Cancer?
There is no single known cause of prostate cancer. Risk increases through a combination of age, inherited factors, family history and other biological and health-related influences. Having one or more risk factors does not mean that a person will develop prostate cancer.
Age
The likelihood of developing prostate cancer increases with age, particularly after age 50. Age is also considered alongside overall health, life expectancy and the biological characteristics of the cancer when determining whether screening, monitoring or treatment may be appropriate.
Family History and Inherited Risk
Having a father, brother or other close relative with prostate cancer can increase risk, particularly when several relatives have been affected or cancer developed at a younger age. Certain inherited genetic changes can also increase susceptibility to prostate cancer and may be associated with more aggressive disease.
For selected patients, genetic counseling or testing may help clarify inherited cancer risk and can provide information relevant to family members. In patients with advanced prostate cancer, genetic and molecular testing may also help identify treatment options.
Race and Ancestry
In the United States, Black men are diagnosed with prostate cancer more often and experience higher prostate cancer mortality than men in other racial and ethnic groups. The reasons are complex and may include biological, genetic, environmental, socioeconomic and healthcare-access factors. Individual risk assessment should consider family history, ancestry, overall health and other clinical factors rather than race alone.
Body Weight and Overall Health
Excess body weight and metabolic health may influence the risk of developing more aggressive prostate cancer and can also affect treatment and recovery. Regular physical activity, a balanced diet, maintaining a healthy weight and managing cardiovascular and metabolic conditions support overall health, although no lifestyle strategy can guarantee that prostate cancer will be prevented.
How Is Prostate Cancer Diagnosed?
Prostate cancer diagnosis usually begins with an assessment of individual risk rather than any single test result. PSA testing, medical and family history, physical examination, prostate imaging and biopsy findings can work together to determine whether cancer is present and, if so, how likely it is to grow or spread.
PSA Blood Testing
Prostate-specific antigen (PSA) is a protein produced by prostate tissue that can be measured with a blood test. An elevated PSA does not necessarily mean that prostate cancer is present. PSA can also be affected by prostate enlargement, inflammation, infection and other factors.
Rather than relying on one universal “normal” PSA value, physicians interpret PSA in the context of age, previous PSA results, prostate size, medications, family history and other risk factors. Depending on the findings, additional testing may be recommended before deciding whether a prostate biopsy is necessary.
Prostate MRI
Multiparametric MRI can provide detailed images of the prostate and identify areas that appear suspicious for clinically significant cancer. MRI findings can help determine whether biopsy is appropriate and can guide targeted tissue sampling when an abnormal area is identified.
MRI/Ultrasound Fusion Biopsy
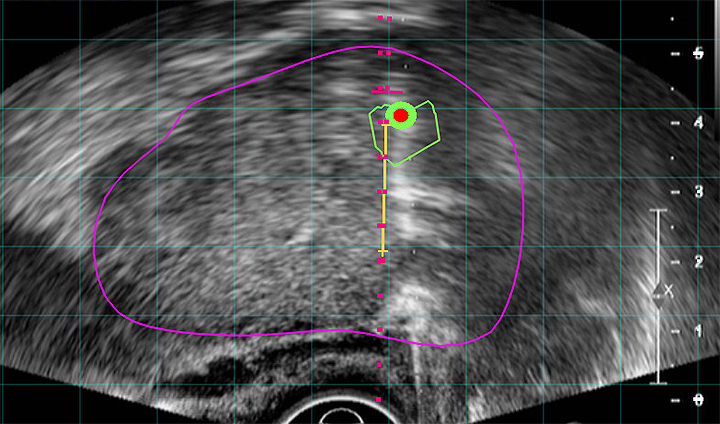
When biopsy is recommended, MRI/ultrasound fusion technology can combine previously obtained MRI images with real-time ultrasound during the procedure. This allows the urologist to target suspicious areas identified on MRI while obtaining the tissue samples needed for pathological evaluation.
At Saint John’s, fusion-guided biopsy technology can help physicians more precisely evaluate suspicious prostate lesions and obtain tissue from areas most important for determining whether clinically significant cancer is present.
Understanding Gleason Score and Grade Group
If prostate cancer is found, a pathologist examines the biopsy tissue to determine how abnormal the cancer cells appear and how the cancer is organized within the prostate tissue. This information is reported using a Gleason score and a corresponding Grade Group.
Grade Groups range from 1 through 5. Grade Group 1 represents cancer with the least aggressive pathological appearance, while higher Grade Groups indicate cancers with features associated with a greater likelihood of growth or spread. Grade Group is considered together with PSA, imaging, tumor extent and other findings when planning care.
How Is Prostate Cancer Staged?
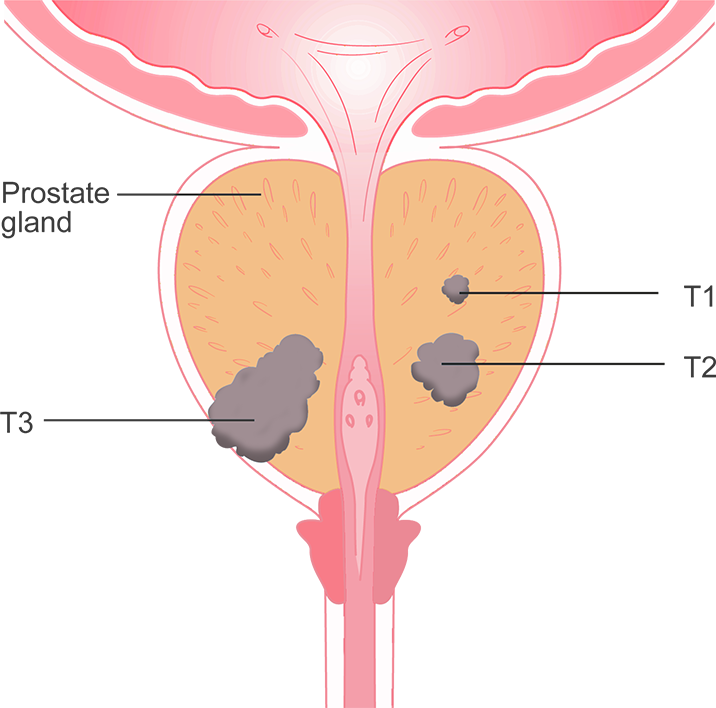
Staging describes the extent of prostate cancer, including whether it remains confined to the prostate, has grown into nearby tissues or has spread to lymph nodes, bones or other parts of the body. Stage is important, but it is only one part of determining how prostate cancer should be managed.
Localized Prostate Cancer
Localized prostate cancer remains within the prostate. Depending on its Grade Group, PSA level, biopsy findings and other characteristics, localized cancer can range from disease appropriate for active surveillance to higher-risk cancer that may benefit from definitive treatment.
Locally Advanced Prostate Cancer
Locally advanced prostate cancer has extended beyond the prostate into nearby tissues or structures. Treatment may involve a combination of therapies depending on the extent of disease and other risk factors.
Metastatic Prostate Cancer
Metastatic prostate cancer has spread beyond the prostate and nearby tissues to distant lymph nodes, bones or other organs. Modern systemic therapies can control metastatic prostate cancer for many patients, and treatment is increasingly personalized according to the disease’s clinical, genetic and molecular characteristics.
PSMA PET and Advanced Imaging
For selected patients, prostate-specific membrane antigen (PSMA) PET imaging can help identify prostate cancer that has spread beyond the prostate or detect sites of disease when cancer is suspected of returning after treatment. Whether PSMA PET or other staging imaging is appropriate depends on the patient’s risk level and clinical circumstances.
Understanding Prostate Cancer Risk
Two patients with prostate cancer at a similar anatomical stage may not have cancers that behave the same way. Physicians combine PSA level, Grade Group, clinical stage, biopsy findings, imaging and other factors to estimate the likelihood that the cancer will grow, recur or spread. This risk assessment helps determine whether active surveillance, surgery, radiation, focal therapy or another treatment approach should be considered.
Personalized Treatment for Localized Prostate Cancer
Not every prostate cancer requires immediate treatment, and there is no single treatment that is right for every patient. Recommendations depend on the cancer’s risk characteristics and extent as well as age, overall health, urinary and sexual function, life expectancy and personal priorities. At Saint John’s, prostate cancer cases can be reviewed through a multidisciplinary approach to help determine which options provide an appropriate balance of cancer control and quality of life.
Active Surveillance for Prostate Cancer
For appropriately selected patients with lower-risk localized prostate cancer, active surveillance can avoid or delay treatment and its potential side effects while continuing to monitor the cancer carefully. Surveillance may include PSA testing, clinical evaluation, prostate imaging and repeat biopsy when appropriate.
Active surveillance differs from simply ignoring prostate cancer. The goal is to identify meaningful changes while the cancer remains treatable and recommend treatment if evidence suggests that the disease is progressing. Watchful waiting is a different, generally less intensive approach in which treatment is directed toward symptoms if they develop.
Robotic Radical Prostatectomy
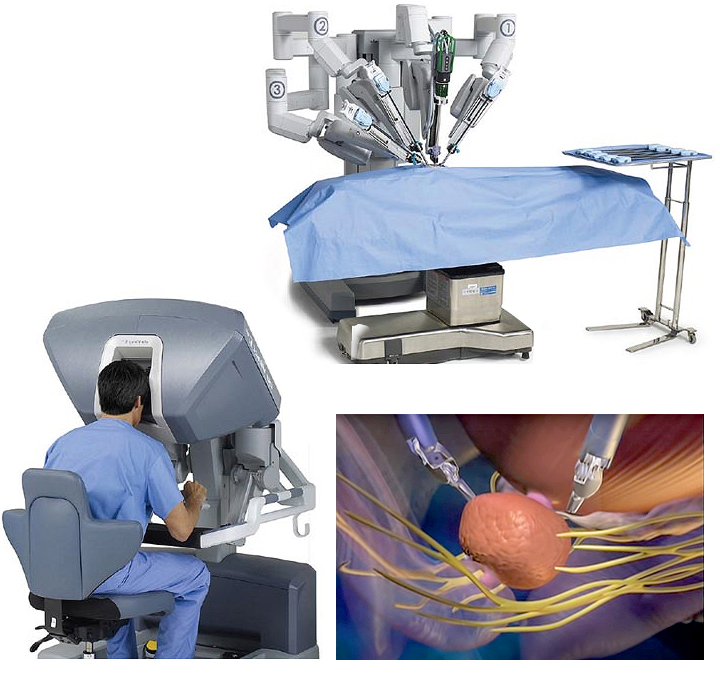
A radical prostatectomy removes the prostate gland and seminal vesicles and may include removal of nearby lymph nodes when appropriate. Surgery can provide definitive treatment for selected patients with localized or locally advanced prostate cancer.
Saint John’s specializes in minimally invasive, robot-assisted prostate cancer surgery. During robotic prostatectomy, the surgeon controls specialized instruments from a surgical console, providing magnified three-dimensional visualization and precise movement through small incisions. Surgical planning considers cancer control as well as preservation of urinary and sexual function whenever safely possible.
Radiation Therapy for Prostate Cancer
Radiation therapy can provide definitive treatment for localized prostate cancer and is also used for selected patients with locally advanced disease. Depending on the cancer’s risk characteristics, radiation may be used alone or combined with androgen deprivation therapy. Radiation can also have important roles when prostate cancer recurs after surgery or has spread beyond the prostate.

External Beam Radiation Therapy
External beam radiation therapy uses advanced imaging and treatment planning to deliver radiation to the prostate and other areas at risk while limiting radiation exposure to nearby healthy tissues. The treatment schedule and radiation technique are individualized according to the patient’s cancer and treatment plan.
Brachytherapy
Brachytherapy delivers radiation from radioactive sources placed within the prostate. It can be used for selected patients as a primary treatment or as part of a combined treatment strategy depending on prostate anatomy, cancer risk and other clinical factors.
Protecting Healthy Tissue During Radiation
The rectum is located immediately behind the prostate and can receive radiation exposure during prostate treatment. For selected patients, SpaceOAR Hydrogel can be placed temporarily between the prostate and rectum to increase separation and help reduce radiation exposure to the rectum.
Focal Therapy with High-Intensity Focused Ultrasound (HIFU)
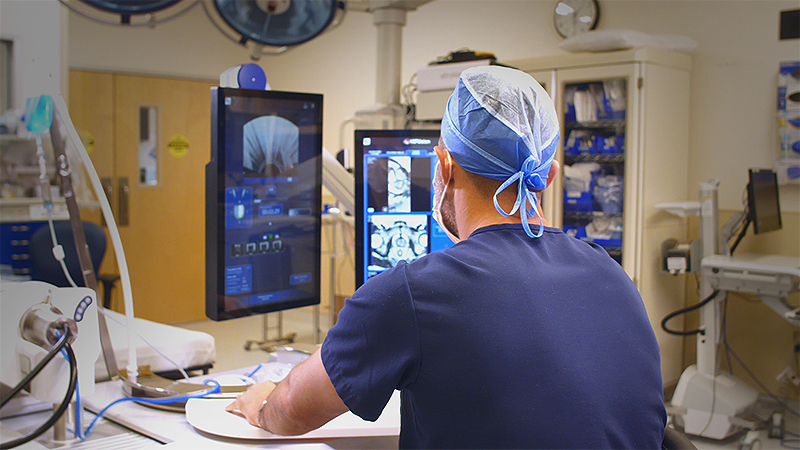
High-intensity focused ultrasound (HIFU) uses precisely directed ultrasound energy to heat and destroy targeted prostate tissue without a surgical incision. Focal treatment is designed to treat the identified area of cancer while preserving surrounding prostate tissue when clinically appropriate.
Saint John’s offers the Focal One system for selected patients with localized prostate cancer. HIFU is not appropriate for every prostate cancer, and patients considering focal therapy should understand the benefits, limitations and need for continued prostate cancer surveillance after treatment.
Learn more: High-Intensity Focused Ultrasound (HIFU) for Prostate Cancer
Related FAQs: Focal One HIFU Frequently Asked Questions
Treatment for Advanced and Recurrent Prostate Cancer
Prostate cancer that has spread beyond the prostate or returned after initial treatment may require a different treatment strategy than localized disease. Advances in hormonal therapy, chemotherapy, targeted treatment, radiopharmaceutical therapy and molecular testing have expanded the options available for advanced prostate cancer. Treatment may involve several therapies over time or a combination of treatments selected according to how the cancer is responding.
Androgen Deprivation Therapy
Prostate cancer cells commonly depend on male hormones called androgens, particularly testosterone, to support their growth. Androgen deprivation therapy (ADT) reduces androgen levels or blocks their effects and is a foundational treatment for many patients with advanced prostate cancer.
ADT may also be combined with radiation therapy for selected patients with intermediate- or high-risk localized or locally advanced prostate cancer. The timing and duration of therapy depend on the cancer’s risk characteristics and treatment plan.
Advanced Hormonal Therapy
Newer androgen-receptor pathway therapies can suppress prostate cancer more effectively than traditional hormone therapy alone for many patients with advanced disease. These treatments may be combined with ADT depending on whether the cancer is newly metastatic, has become resistant to traditional hormonal treatment or has other clinical characteristics that influence treatment selection.
Chemotherapy
Chemotherapy can be used for selected patients with metastatic or advanced prostate cancer. Its role depends on the extent of disease, previous treatment, overall health and whether the cancer remains sensitive to hormonal therapy. In some patients with newly diagnosed metastatic disease, chemotherapy may be incorporated into an intensified treatment strategy rather than waiting until later in the course of the disease.
Genetic and Molecular Testing
Inherited genetic testing and molecular testing of the cancer can provide information that affects treatment for some patients with advanced prostate cancer. Testing may identify genetic and molecular changes associated with DNA repair or other cancer pathways that make the cancer more likely to respond to a particular targeted therapy.
Inherited findings can also have implications for relatives, making genetic counseling an important part of care for selected patients and families.
Targeted Therapy
Targeted therapies act on specific vulnerabilities within cancer cells rather than treating all rapidly dividing cells in the same way. For selected advanced prostate cancers with particular genetic and molecular changes, targeted treatments such as PARP inhibitors may become part of the treatment strategy.
PSMA-Targeted and Radiopharmaceutical Therapy
Some advanced prostate cancers express prostate-specific membrane antigen (PSMA), which can be used not only to locate disease through PSMA PET imaging but also to direct treatment to cancer cells. For appropriately selected patients, PSMA-targeted radiopharmaceutical therapy can deliver radiation directly to sites of prostate cancer throughout the body.
Other radiopharmaceutical treatments may also be used in selected patients when prostate cancer has spread to bone. Eligibility depends on the disease pattern, previous treatment and other clinical factors.
Radiation and Treatment of Metastatic Sites
Radiation therapy can be used in advanced prostate cancer to control specific areas of disease, relieve symptoms such as bone pain or address sites that require additional local treatment. In selected patients, treatment directed at particular metastatic sites may be incorporated into a broader systemic treatment plan.
Personalized Prostate Cancer Care at Saint John’s
Choosing a prostate cancer treatment involves more than determining whether cancer is present. Our specialists consider how likely the cancer is to progress, whether it remains localized, the patient’s overall health and life expectancy, and how different treatments may affect urinary, sexual and bowel function. This allows treatment recommendations to reflect both cancer control and the patient’s quality-of-life priorities.
Multidisciplinary Treatment Planning
Prostate cancer care can involve specialists in urologic oncology, radiation oncology, medical oncology, imaging, pathology and other disciplines. Multidisciplinary review allows specialists to consider different treatment approaches together, particularly when more than one option may provide effective cancer control.
Protecting Urinary and Sexual Health
Prostate cancer and its treatment can affect urinary control, erectile function and other aspects of sexual health. These considerations are incorporated into treatment planning whenever possible, and patients who experience changes after treatment can be evaluated for therapies that support recovery and long-term quality of life.
You can learn more about the evaluation and treatment of erectile dysfunction, including options for men whose erectile function has changed following prostate cancer treatment.
Research and Evolving Treatment Options
Prostate cancer treatment continues to evolve through advances in imaging, surgical and radiation techniques, genetic and molecular testing, systemic therapy and clinical research. These developments are allowing physicians to distinguish cancers that can be safely monitored from those requiring treatment and to personalize therapy more precisely when prostate cancer becomes advanced or recurrent.
Clinical trials continue to evaluate new combinations and sequences of hormonal therapy, targeted treatment, immunotherapy, radiopharmaceutical therapy and other approaches for prostate cancer. Participation in a clinical trial may provide access to an investigational strategy while helping researchers determine how prostate cancer treatment can be improved for future patients.
For some patients, the appropriate decision may be active surveillance. For others, surgery, radiation, focal therapy or a combination of treatments may offer the most appropriate approach. Patients with advanced or recurrent disease may have additional systemic and targeted treatment options based on the characteristics of their cancer.

Our goal is not simply to choose the most aggressive treatment available, but to identify the treatment strategy that appropriately matches the cancer while considering the patient’s health, priorities and long-term well-being.
If you have been diagnosed with prostate cancer, have an elevated PSA or are seeking another opinion, our prostate cancer specialists can help you understand your diagnosis, evaluate your options and develop a treatment plan personalized to you.
If you have questions regarding prostate cancer treatments, your Gleason score, or PSA, please call today.



