
What Is Lung Cancer?
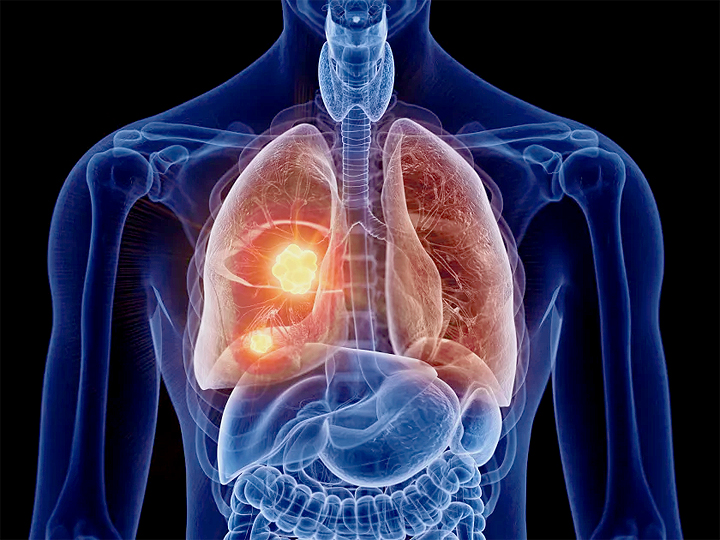
Lung cancer develops when abnormal cells within the lungs grow uncontrollably and form a malignant tumor. These cancer cells can invade surrounding lung tissue and, as the disease progresses, may spread through the lymphatic system or bloodstream to lymph nodes and other parts of the body.
There are two main types of lung cancer: non-small cell lung cancer (NSCLC) and small cell lung cancer (SCLC). Smoking remains the leading risk factor, but lung cancer can also develop in people who have never smoked. Advances in screening, imaging, molecular testing, minimally invasive procedures, targeted therapies, immunotherapy, radiation therapy, and surgery have significantly changed how lung cancer is detected and treated.
Understanding Lung Cancer Risk and Symptoms
Anyone can develop lung cancer, although certain exposures, medical history, and inherited or acquired factors can increase risk. Recognizing risk is particularly important because early lung cancer may cause few or no symptoms, and screening with low-dose CT may allow cancer to be detected earlier in people who meet established high-risk criteria.
Who Is at Risk for Lung Cancer?
Cigarette smoking is the most important risk factor for lung cancer, and risk generally increases with the amount and duration of tobacco exposure. However, former smokers remain at increased risk after quitting, and lung cancer can also occur in people who have never smoked.
Other factors that may increase the risk of developing lung cancer include secondhand tobacco smoke, radon, certain workplace and environmental exposures, previous radiation therapy to the chest, and a personal or family history of lung cancer.

Environmental and Occupational Risk Factors
Long-term exposure to certain cancer-causing substances can increase lung cancer risk. Some of these exposures occur in workplaces, while others may be present in homes or the surrounding environment.
- Radon – A naturally occurring radioactive gas that can accumulate inside homes and buildings and is an important cause of lung cancer in people who smoke and those who have never smoked.
- Asbestos – Occupational exposure can increase the risk of lung cancer, particularly when combined with smoking.
- Diesel exhaust – Long-term occupational exposure is associated with increased lung cancer risk.
- Arsenic, chromium, nickel, and certain forms of silica – Exposure to these substances in some workplaces can increase lung cancer risk.
- Air pollution – Long-term exposure to higher levels of outdoor air pollution is associated with an increased risk of lung cancer.
Lung Cancer in People Who Have Never Smoked
Lung cancer should not be considered exclusively a smoking-related disease. People who have never smoked can develop lung cancer as a result of factors that may include radon, secondhand smoke, air pollution, occupational exposures, inherited susceptibility, or molecular changes that develop within lung cells.
In many people who have never smoked, no single cause can be identified. This distinction is increasingly important because the biology of an individual lung cancer—not simply a patient’s smoking history—can influence treatment decisions.
Signs and Symptoms of Lung Cancer
Early lung cancer may not cause noticeable symptoms. When symptoms develop, they can vary according to the tumor’s location, size, and whether cancer has affected nearby structures or spread to other parts of the body.

Signs and symptoms may include:
- A new or persistent cough that does not go away
- A chronic cough that changes or worsens
- Coughing up blood or blood-streaked mucus
- Shortness of breath or difficulty breathing
- Chest pain or discomfort
- Wheezing or hoarseness
- Repeated pneumonia or other respiratory infections
- Unexplained weight loss or loss of appetite
- Persistent fatigue or weakness
Symptoms such as bone pain, persistent headaches, neurologic changes, enlarged lymph nodes, or other new problems can sometimes occur when lung cancer has spread beyond the lungs. These symptoms can also be caused by many conditions other than cancer, but persistent or unexplained changes should be medically evaluated.
Types of Lung Cancer
Determining the type of lung cancer is an essential part of diagnosis because different cancers can behave differently and respond to different treatments. Lung cancers are broadly divided into non-small cell lung cancer (NSCLC) and small cell lung cancer (SCLC), with NSCLC accounting for most cases.
Pathologists examine tumor tissue to determine the cancer type and subtype. For many patients, particularly those with non-small cell lung cancer, additional biomarker or molecular testing can identify characteristics of the tumor that may help guide treatment.
Non-Small Cell Lung Cancer (NSCLC)
Non-small cell lung cancer is the most common major category of lung cancer and includes several different tumor types. The three principal subtypes are adenocarcinoma, squamous cell carcinoma, and large cell carcinoma.
Adenocarcinoma
Adenocarcinoma is the most common subtype of non-small cell lung cancer. It often develops in the outer portions of the lung and occurs in people who currently smoke, previously smoked, and those who have never smoked. Adenocarcinoma begins in glandular epithelial cells, including cells capable of producing substances such as mucus.
Squamous Cell Carcinoma
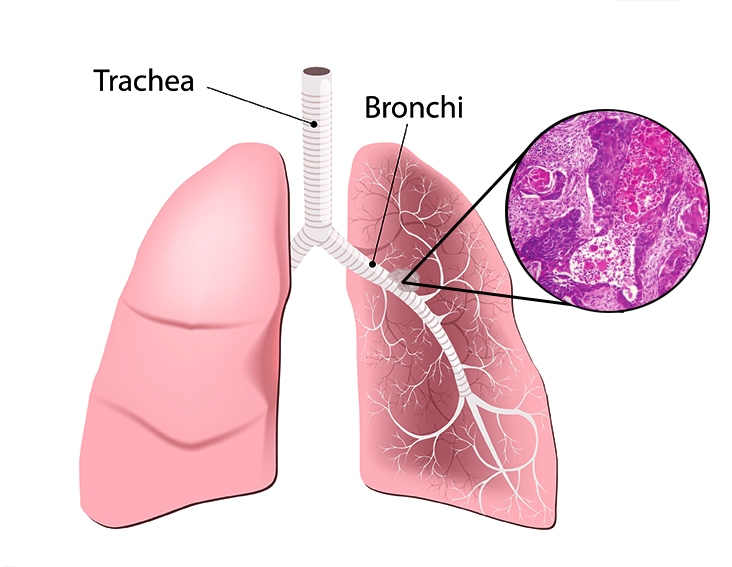
Squamous cell carcinoma develops from squamous cells lining the airways and is more strongly associated with tobacco exposure than some other forms of NSCLC. These tumors frequently arise in the central portions of the lung near the larger airways, although their location and presentation can vary.
Large Cell Carcinoma and Other NSCLC Types
Large cell carcinoma is a less common form of non-small cell lung cancer that can occur in different areas of the lung. Additional uncommon NSCLC types and mixed histologies can also occur, making examination of tumor tissue by a pathologist important for accurate classification.
Small Cell Lung Cancer (SCLC)
Small cell lung cancer is a less common but generally faster-growing form of lung cancer that has a greater tendency to spread earlier in its course. It is strongly associated with tobacco exposure and is treated differently from most non-small cell lung cancers.
Small cell lung cancer has traditionally been described as limited-stage or extensive-stage disease. Limited-stage disease is confined to an area that can generally be encompassed within a single radiation treatment field, while extensive-stage disease has spread beyond that region. More detailed TNM staging may also be used as part of the clinical evaluation.
Lung Cancer Diagnosis
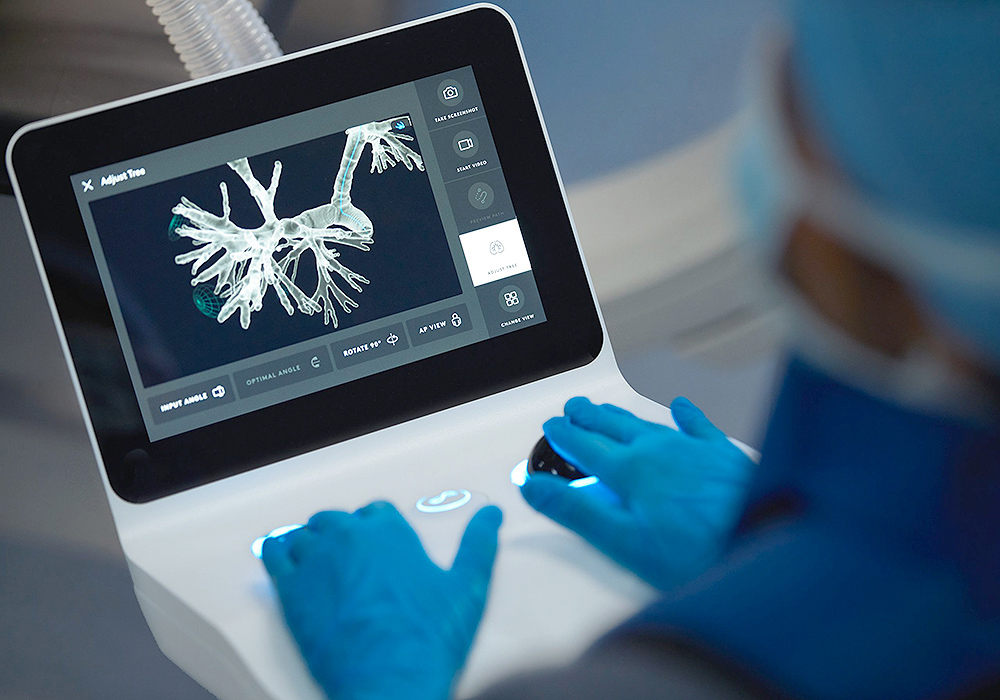
Diagnosing lung cancer involves determining whether a suspicious area in the lung is cancerous, identifying the type of cancer, and establishing how far the disease has spread. The evaluation may combine advanced imaging, minimally invasive biopsy techniques, bronchoscopy, lymph-node sampling, laboratory analysis, and molecular testing to provide the information needed to develop an individualized treatment plan.
The diagnostic pathway differs from one patient to another. The location and size of a lung nodule or mass, nearby lymph nodes, other imaging findings, overall health, and the amount of tissue needed for diagnosis and biomarker testing can all influence which procedure is most appropriate.
Imaging for Lung Cancer
Chest imaging often provides the first indication of a suspicious lung nodule or mass. CT scans provide detailed images of the lungs and surrounding structures and can help physicians evaluate the size, shape, and location of an abnormality as well as enlarged lymph nodes or other findings.
Additional imaging may be used when lung cancer is suspected or confirmed. PET/CT can help evaluate whether cancer may have spread to lymph nodes or other parts of the body, while MRI is particularly useful when detailed imaging of the brain or certain other structures is needed. Imaging findings also help physicians determine the safest and most effective way to obtain tissue for diagnosis.
Robotic and Navigational Bronchoscopy
Advanced bronchoscopy can help pulmonologists reach suspicious nodules located in peripheral or difficult-to-access areas of the lung. Robotic and navigational bronchoscopy use detailed imaging and computer-assisted guidance to direct specialized instruments through the airways toward the abnormality, where tissue samples can be obtained.
These minimally invasive approaches can provide access to some lung nodules without requiring an incision through the chest wall. The most appropriate biopsy technique depends on the nodule’s location, size, surrounding anatomy, and other clinical factors.
Bronchoscopy
During bronchoscopy, a thin, flexible instrument equipped with a camera is passed through the mouth or nose and into the airways. Physicians can examine the trachea and bronchial tubes and obtain tissue or fluid samples from suspicious areas.
Bronchoscopy can also serve as a platform for advanced diagnostic techniques, including robotic or navigational bronchoscopy and endobronchial ultrasound.
Endobronchial Ultrasound (EBUS)
Endobronchial ultrasound combines bronchoscopy with ultrasound imaging to visualize structures and lymph nodes adjacent to the airways. A needle can be guided through the airway wall to obtain tissue from mediastinal or hilar lymph nodes and selected lung lesions.
EBUS can be especially valuable because lymph-node sampling can help establish both a diagnosis and the stage of lung cancer while avoiding a more invasive surgical procedure in many patients.
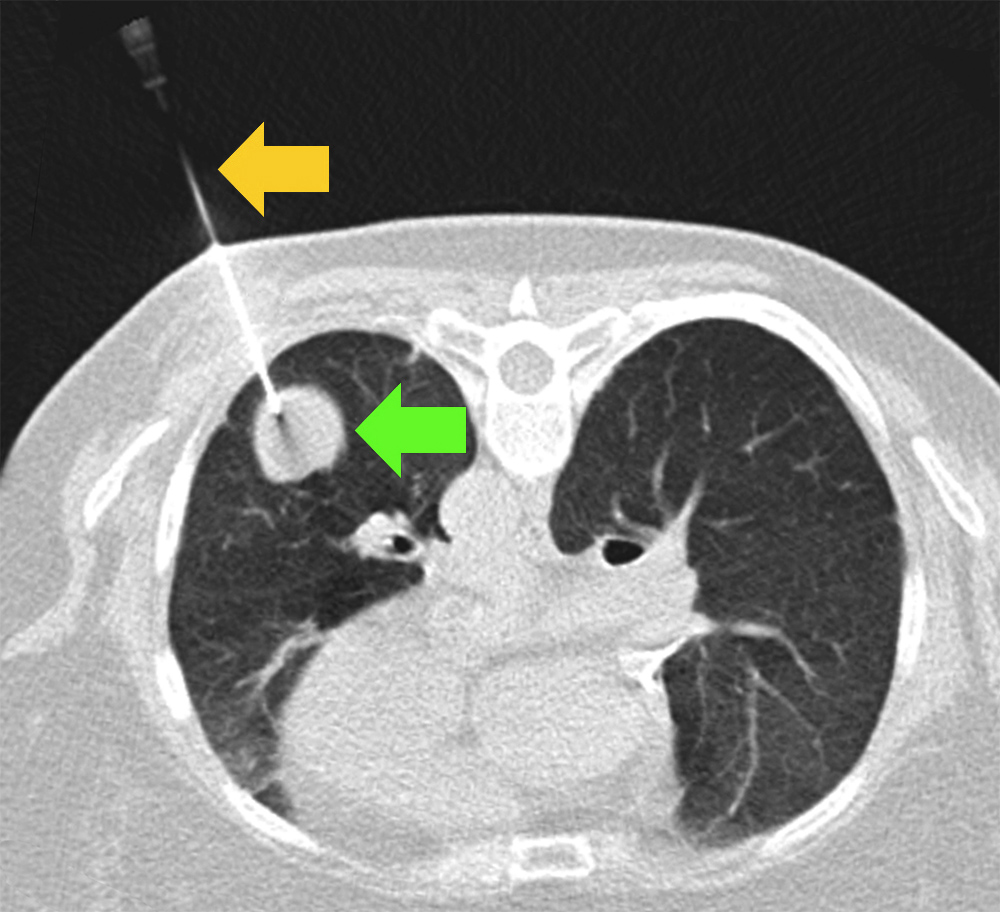
CT-Guided Needle Biopsy
For some lung nodules or masses, particularly those located near the outer portion of the lung, a needle biopsy through the chest wall may provide the most direct route to obtain tissue. CT imaging is used to guide the needle accurately into the abnormality.
The tissue is then examined by a pathologist to determine whether cancer is present and, when possible, identify the tumor type and characteristics needed for treatment planning.
Thoracentesis and Pleural Fluid Testing
When fluid has accumulated in the pleural space surrounding the lung, thoracentesis may be performed to remove a sample using a needle or small catheter. The fluid can be examined for cancer cells as well as other causes of pleural effusion.
Finding malignant cells in pleural fluid can provide important diagnostic and staging information and may influence treatment planning.
Surgical Biopsy
If a diagnosis cannot be adequately established with less invasive techniques, surgical biopsy may occasionally be necessary. Video-assisted thoracic surgery (VATS) or robotic thoracic surgery can allow a surgeon to obtain tissue through small incisions in the chest.
In selected patients with a highly suspicious, potentially early-stage lung tumor, the diagnostic procedure may be planned together with surgical removal of the tumor when appropriate. This decision depends on imaging, lung function, surgical candidacy, and the likelihood that the abnormality represents cancer.
Mediastinoscopy
Mediastinoscopy is a surgical procedure used to obtain tissue from lymph nodes in the mediastinum, the central area of the chest between the lungs. Although EBUS now allows many mediastinal lymph nodes to be sampled less invasively, mediastinoscopy remains useful in selected situations when additional or confirmatory lymph-node evaluation is needed.
Pathology and Biomarker Testing
Obtaining tissue is only one part of modern lung cancer diagnosis. A pathologist examines the sample to determine whether cancer is present and identify its type and subtype. For many patients with non-small cell lung cancer, tumor tissue may also undergo molecular or biomarker testing to identify characteristics that can help guide treatment.
Depending on the type and stage of lung cancer, testing may evaluate molecular alterations and biomarkers associated with response to targeted therapies or immunotherapy. This information increasingly allows treatment to be selected according to the biology of an individual tumor rather than relying on cancer stage and appearance alone.
Liquid Biopsy
A liquid biopsy analyzes material released by cancer cells into the bloodstream, such as circulating tumor DNA. In selected patients with lung cancer, blood-based molecular testing can complement tissue testing and help identify tumor alterations that may influence treatment.
Liquid biopsy does not replace tissue biopsy in every patient and has limitations, including the possibility that a tumor may not release enough detectable material into the bloodstream. Physicians determine when blood-based testing can provide useful additional information alongside imaging, pathology, and tissue-based molecular testing.
How Is Lung Cancer Staged?
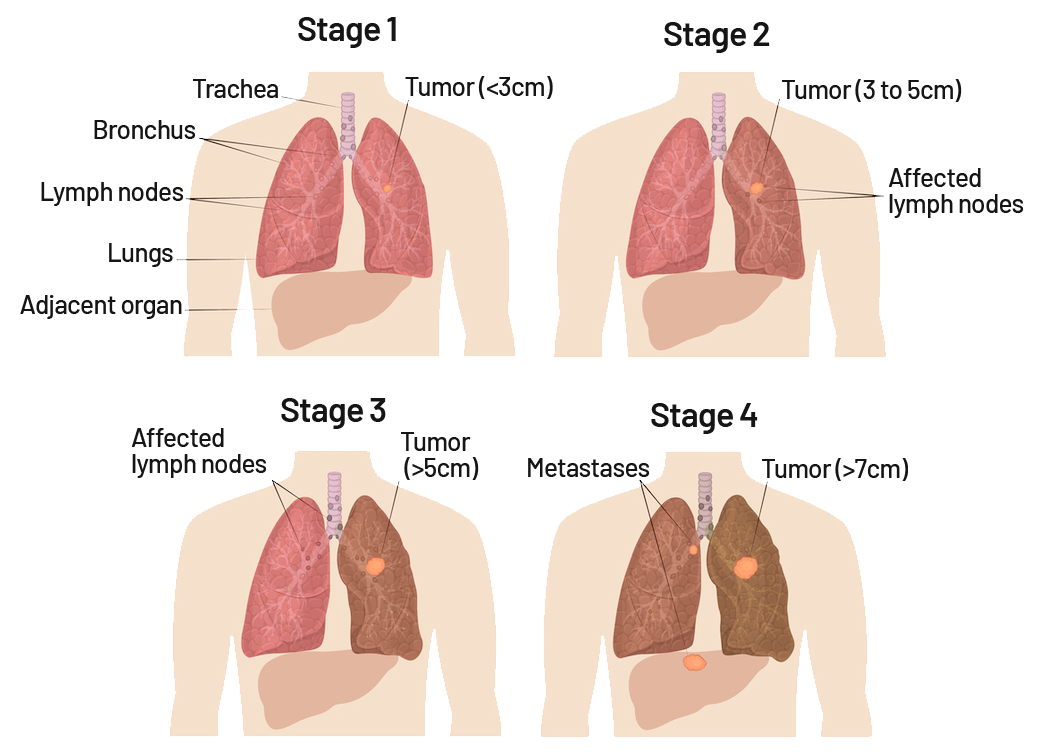
After lung cancer is diagnosed, physicians determine its stage to understand how much cancer is present and whether it has spread. Staging is one of the most important factors in treatment planning and may incorporate information from CT, PET/CT, MRI, lymph-node sampling, biopsy, and surgery.
Non-small cell lung cancer is staged using the TNM system. The T describes the size and local extent of the primary tumor, N describes whether cancer has spread to regional lymph nodes, and M describes whether cancer has spread to distant sites. These findings are combined to assign an overall stage. :contentReference[oaicite:1]{index=1}
Stage 0 Lung Cancer
Stage 0, also called carcinoma in situ, is the earliest stage of non-small cell lung cancer. Abnormal cancerous cells are limited to the surface lining of the airways or lung tissue and have not invaded deeper tissues or spread to lymph nodes or distant parts of the body. :contentReference[oaicite:2]{index=2}
Stage I Lung Cancer
Stage I non-small cell lung cancer is generally confined to the lung and has not spread to regional lymph nodes or distant organs. Stage I is divided into additional subgroups according to tumor size and other characteristics. Many patients with Stage I disease may be candidates for treatment intended to cure the cancer, including surgery or other localized treatments when surgery is not appropriate.
Stage II Lung Cancer
Stage II lung cancer remains confined to the chest but may involve a larger or more locally invasive primary tumor, nearby lymph nodes, or particular combinations of tumor and lymph-node involvement. Treatment often involves a combination of therapies selected according to the exact stage, tumor characteristics, and the patient’s overall health.
Stage III Lung Cancer
Stage III lung cancer is locally advanced disease involving more extensive structures or lymph nodes within the chest but without distant metastatic spread. Stage III encompasses a wide range of disease, and determining exactly which lymph nodes and structures are involved is particularly important because treatment can vary considerably among patients.
Stage IV Lung Cancer
Stage IV lung cancer has spread beyond the original lung and regional lymph nodes to another part of the body, to the opposite lung, or in certain circumstances to the fluid surrounding the lung or heart. Common sites of distant spread can include the brain, bones, liver, and adrenal glands. Stage IV is subdivided further according to the pattern and extent of metastatic disease. :contentReference[oaicite:3]{index=3}
When lung cancer spreads to another organ, it remains lung cancer. For example, lung cancer that spreads to the liver is metastatic lung cancer rather than liver cancer because the cancer cells originated in the lung. Treatment therefore continues to be based on the type and molecular characteristics of the lung cancer as well as the extent and location of metastatic disease.
Small Cell Lung Cancer Staging
Small cell lung cancer can also be described using TNM staging, but clinicians commonly classify it as limited-stage or extensive-stage disease for treatment planning. Limited-stage disease can generally be encompassed within a defined radiation treatment area, while extensive-stage disease has spread beyond that region. :contentReference[oaicite:4]{index=4}
Lung Cancer Treatment
Treatment for lung cancer is personalized according to the type and stage of cancer, its molecular and biomarker characteristics, where it is located, and a patient’s overall health and lung function. Depending on these factors, treatment may include surgery, radiation therapy, chemotherapy, immunotherapy, targeted therapy, or a combination of approaches.
For some patients, treatment is focused on removing or eliminating a localized cancer. For others, medications that travel throughout the body are used to control cancer cells wherever they may be present. Treatments may also be given before or after surgery to reduce the risk of cancer returning. A multidisciplinary lung cancer team can help determine which approach, or combination of treatments, is most appropriate.

Lung Cancer Surgery
Surgery may be recommended when lung cancer can be completely removed and a patient has adequate lung function to safely undergo an operation. It is most commonly used for earlier-stage non-small cell lung cancer, although surgery may also be appropriate in selected patients with more complex disease.
The amount of lung removed depends on the tumor’s size and location, the patient’s lung function, and other clinical factors. Procedures can range from removal of a small portion of lung to a segmentectomy, lobectomy, or, less commonly, removal of an entire lung. Whenever appropriate, minimally invasive approaches such as video-assisted thoracic surgery (VATS) or robotic thoracic surgery may be used.
Radiation Therapy
Radiation therapy uses precisely directed high-energy radiation to damage cancer cells while limiting exposure to surrounding healthy tissue. It can be used at different stages of lung cancer and may be given alone or together with chemotherapy, immunotherapy, surgery, or other treatments.
For some patients with early-stage lung cancer who cannot undergo surgery, highly focused radiation can provide a nonsurgical treatment option. Radiation may also be used for locally advanced cancer or to treat specific areas where cancer has spread and relieve symptoms.
Chemotherapy
Chemotherapy uses medications that travel through the bloodstream to destroy cancer cells or prevent them from growing and dividing. It remains an important treatment for both non-small cell and small cell lung cancer and is frequently combined with other therapies.
Depending on the type and stage of cancer, chemotherapy may be given before surgery to help shrink a tumor, after surgery to reduce the risk of recurrence, together with radiation therapy, or as part of treatment for advanced disease.
Immunotherapy
Immunotherapy helps the body’s immune system recognize and attack cancer cells. Immune checkpoint inhibitors have become an important part of lung cancer treatment and may be used alone or in combination with chemotherapy and other treatments, depending on the type and stage of cancer and characteristics of the tumor.
Immunotherapy can be used for some patients with advanced lung cancer and increasingly plays a role before or after surgery for selected patients with potentially curable non-small cell lung cancer. It is also used with chemotherapy for many patients with extensive-stage small cell lung cancer.
Targeted Therapy
Some lung cancers contain specific genetic or molecular changes that help the cancer grow. Targeted therapies are designed to interfere with these changes or the proteins they produce, allowing treatment to focus on particular characteristics of an individual tumor.
Biomarker testing can help determine whether a patient’s cancer has a change for which a targeted treatment is available. Targeted therapies are particularly important in many forms of non-small cell lung cancer and may be used for advanced disease as well as before or after surgery in selected patients.
Supportive and Palliative Care
Supportive and palliative care can be provided throughout lung cancer treatment to help manage symptoms and treatment side effects and support quality of life. This care may address pain, breathing difficulties, fatigue, nutrition, emotional well-being, and other needs and can be provided alongside treatments intended to control or eliminate the cancer.
Learn More About Lung Cancer Treatment
Because lung cancer treatment can involve several specialties and different combinations of therapy, treatment planning is individualized for each patient. Learn more about surgical and nonsurgical treatment options, minimally invasive thoracic surgery, and other approaches available through our lung cancer program.
If you have questions regarding Lung Cancer Screening or Treatment, please call today. Click here to request an appointment.



